|
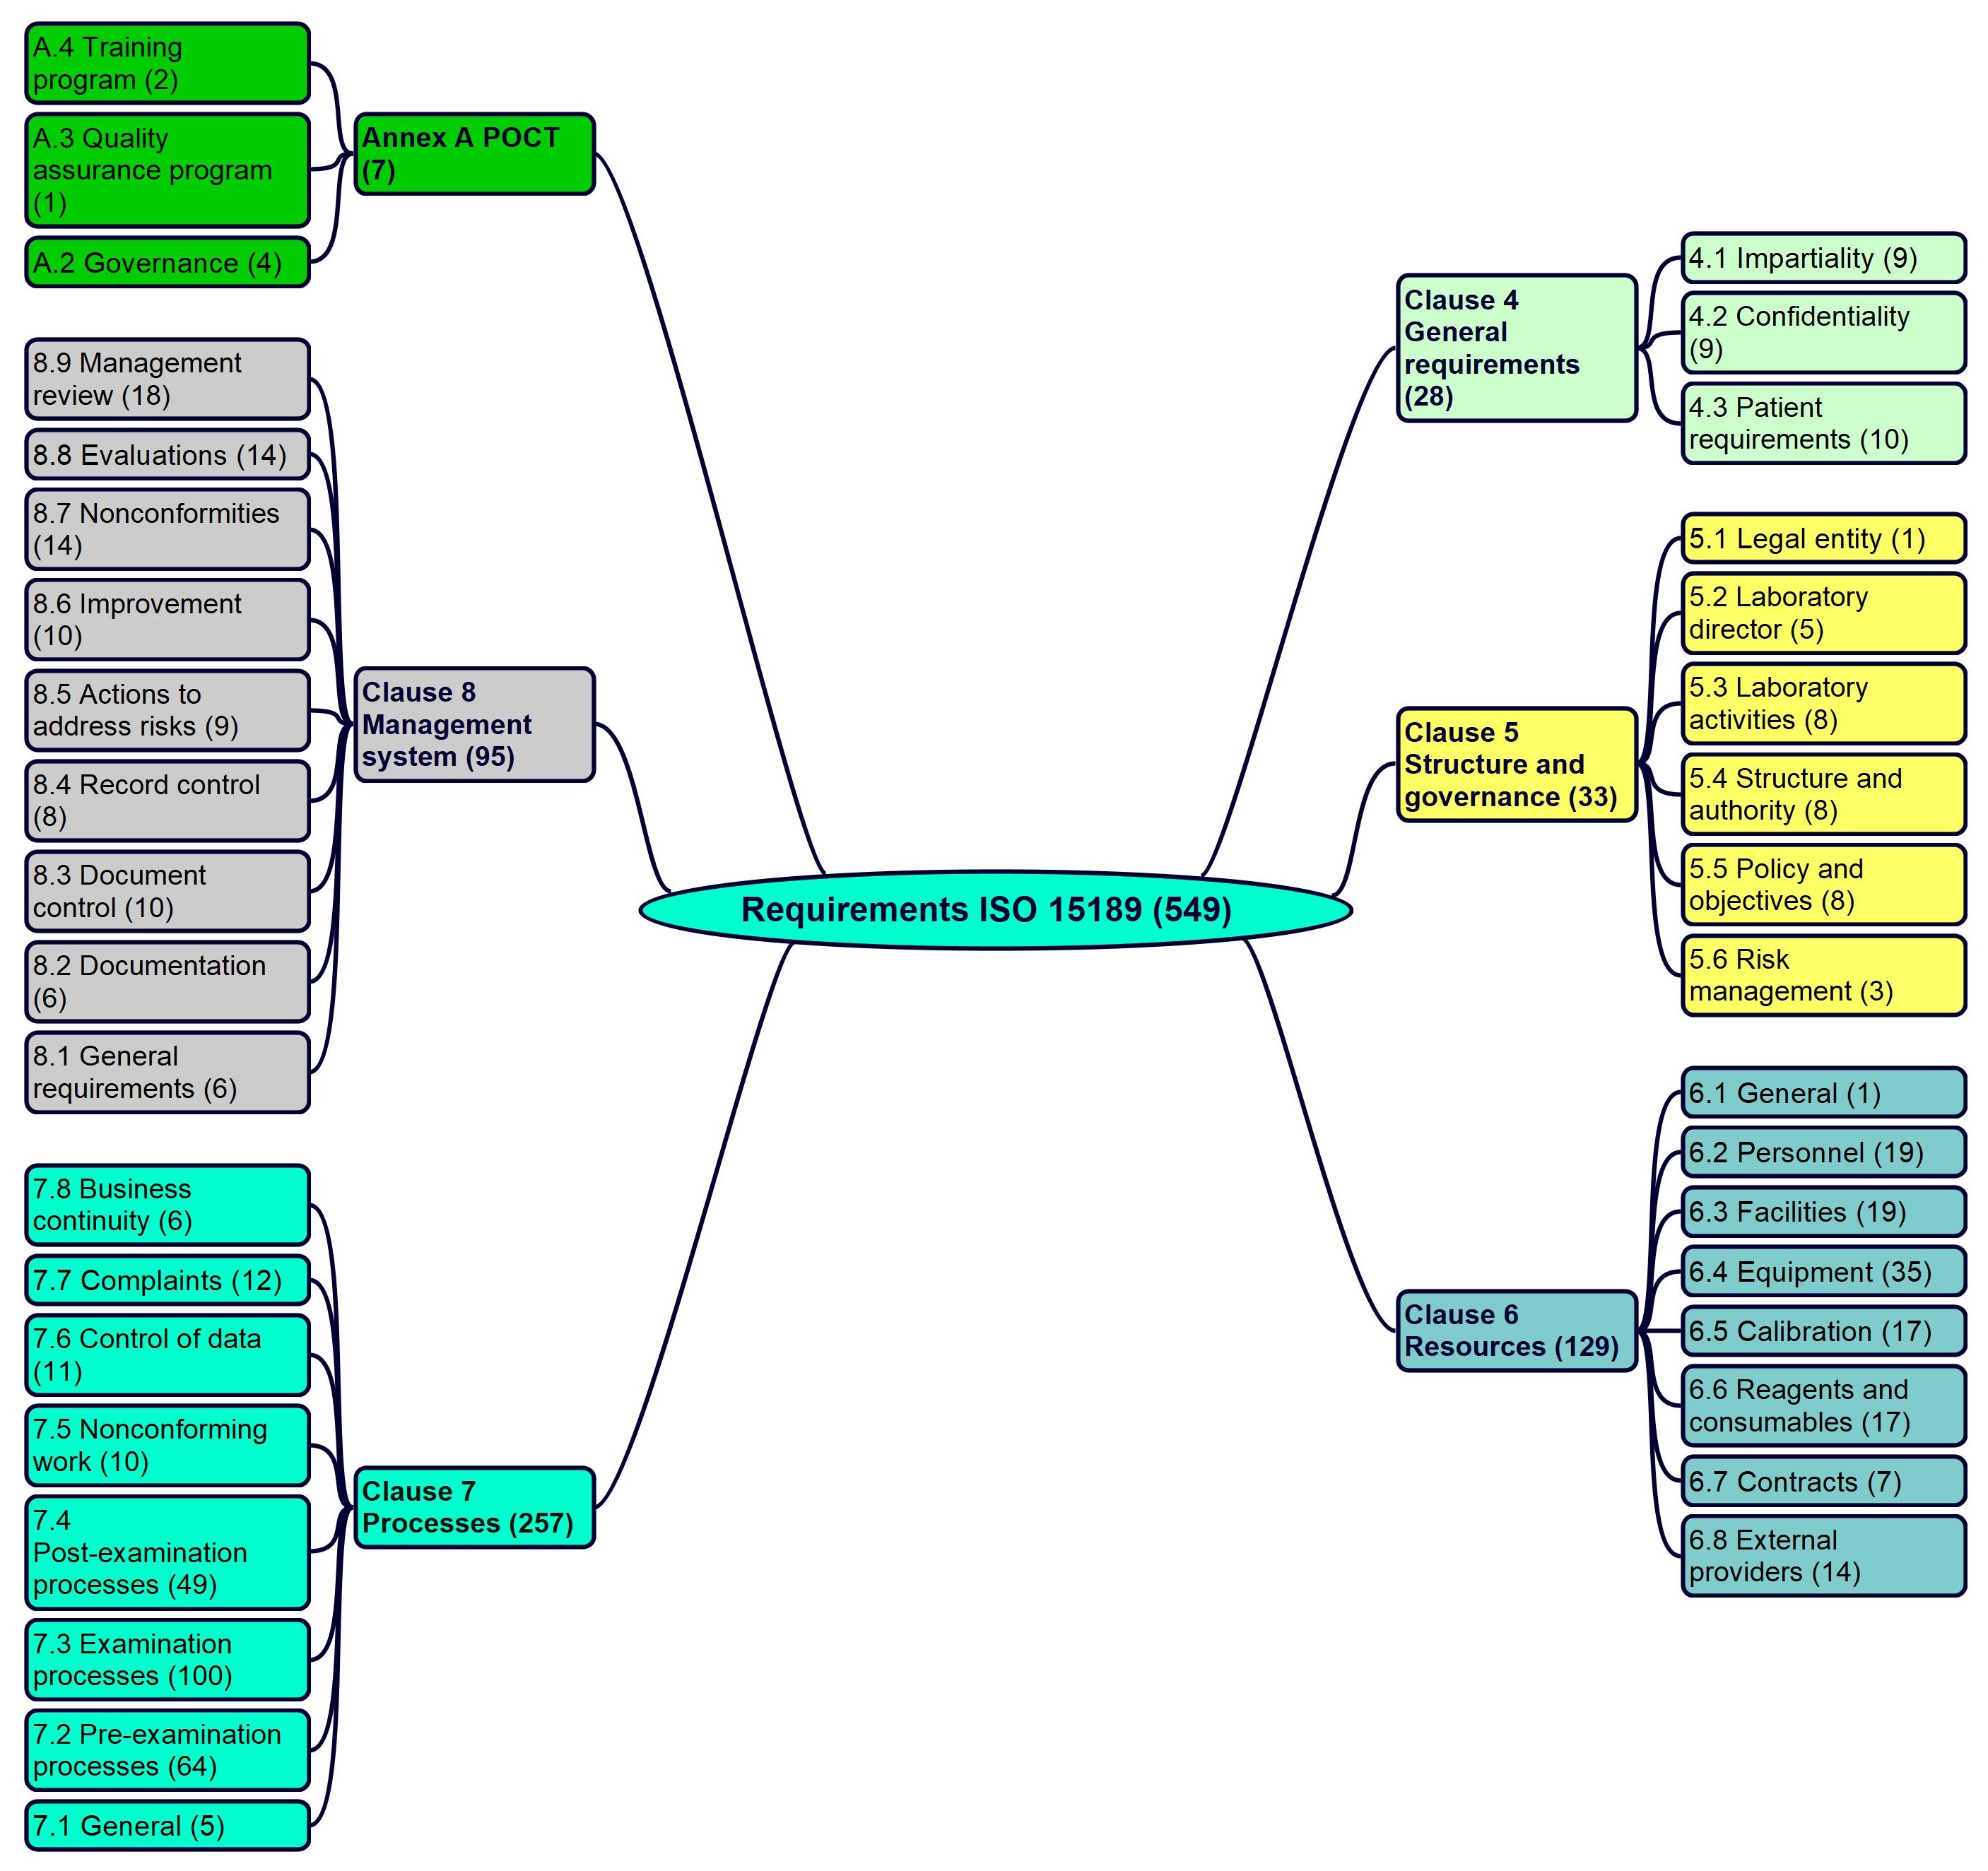
ISO 15189 - Requirements and comments regarding quality and competence
|
|
|
Clause and sub-clause
|
Requirement
|
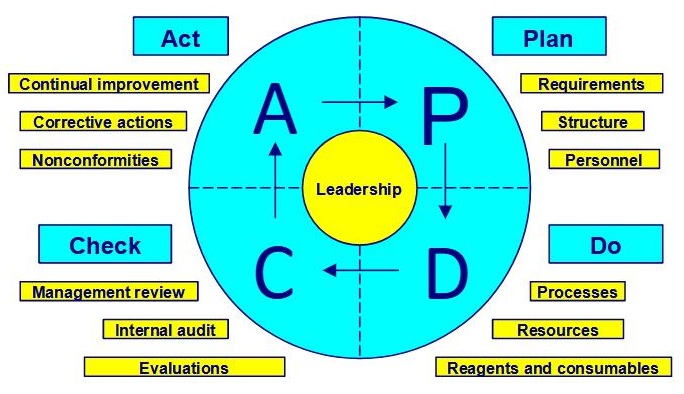
PDCA cycle, links, comments
|
|
|
General requirements
|
|
|
|
4.1
|
Impartiality
|
|
|
1
|
4.1 a
|
Carry out laboratory activities impartially |
Top management responsibility, cf. § 5.2.2 |
|
2
|
4.1 a
|
Structure and manage laboratory to safeguard impartiality |
Top management responsibility, cf. § 5.2.2 |
|
3
|
4.1 b
|
Commit to carrying out activities impartially |
Documented commitment by laboratory top management, cf. § 8.2.3 (quality policy) |
|
4
|
4.1 c
|
Assume responsibility for its activities |
By the laboratory |
|
5
|
4.1 c
|
Prevent pressures from compromising the impartiality of laboratory activities |
Such as commercial, financial, ownership, ownership, governance, management, personnel or other pressures |
|
6
|
4.1 d
|
Monitor activities and relationships |
In order to identify threats to impartiality. Top management responsibility, cf. § 5.2.2 |
|
7
|
4.1 d
|
Include relationships with personnel |
In the monitoring of threats to impartiality |
|
8
|
4.1 e
|
Eliminate or minimize the effect of any threat |
That could compromise laboratory impartiality in order to safeguard impartiality |
|
9
|
4.1 e
|
Be able to demonstrate how a threat is mitigated |
By the laboratory |
| |
4.2
|
Confidentiality
|
|
| |
4.2.1
|
Management of information
|
|
|
10
|
4.2.1
|
Assume responsibility for managing all patient-related information |
Information obtained during the performance of laboratory activities |
| 11 |
4.2.1 |
Ensure that patient information management includes respect for privacy |
And confidentiality |
| 12 |
4.2.1 |
Inform the patient (or user) in advance of the information |
That will be made public |
| 13 |
4.2.1 |
Treat all information as confidential |
Except for information made public (agreement between the laboratory and the patient) |
| |
4.2.2
|
Release of information
|
|
|
14
|
4.2.2
|
Inform the patient of the confidential information that will be disclosed |
By the laboratory, as required by regulations, unless regulations prohibit it |
| 15 |
4.2.2 |
Maintain the confidentiality of patient information obtained from sources other than the patient |
Such as a complainant or regulatory authorities |
| 16 |
4.2.2 |
Do not disclose the identity of the information source |
In order to protect privacy |
| 17 |
4.2.2 |
Do not disclose the identity of the information source to the patient |
Unless an agreement exists with the source |
| |
4.2.3
|
Personnel responsibility
|
|
|
18
|
4.2.3
|
Maintain the confidentiality of all information obtained through laboratory activities. |
This applies to staff, members of governing bodies, contractors, and any external individuals with access to laboratory information |
| |
4.3
|
Requirements regarding patients
|
|
|
19
|
4.3
|
Ensure that patient well-being, safety, and respect for patient rights are prioritized |
This concerns laboratory top management, cf. § 8.4.1 |
| 20 |
4.3 a |
Establish and implement the process seize opportunities |
To provide useful information on the choice of examination methods and the interpretation of examination results., cf. § 8.2.4 |
| 21 |
4.3 b |
Establish and implement the process make public information available |
Regarding the testing process (costs and turnaround time for results), cf. § 8.2.4 |
| 22 |
4.3 c |
Establish and implement the process review periodically examinations offered by the laboratory |
To ensure that examinations are clinically appropriate and necessary, cf. § 8.2.4 |
| 23 |
4.3 d |
Establish and implement the process communicate incidents to stakeholders |
Harmful to patients, and records of the actions implemented to reduce harm,, cf. § 8.2.4 |
| 24 |
4.3 e |
Establish and implement the process handle patients, samples, and anatomical specimens |
With rigorous attention and respect, cf. § 8.2.4 |
| 25 |
4.3 f |
Establish and implement the process obtain formal consent |
When it is a requirement, cf. § 8.2.4 |
| 26 |
4.3 g |
Establish and implement the process maintain the availability of all patient samples |
And the records in the event of laboratory closure, acquisition, or merger., cf. § 8.2.4 |
| 27 |
4.3 h |
Establish and implement the process for communicating information to the patient or a healthcare provider |
At the request of the patient or a healthcare provider acting on their behalf, cf. § 8.2.4 |
| 28 |
4.3 i |
Establish and implement the process respect patient rights |
Free from discrimination, cf. welcome booklet, § 8.2.4 |
|
|
5
|
Structural and governance requirements
|
|
| |
5.1
|
Legal entity
|
|
| 29 |
5.1 |
Ensure that the laboratory is an entity legally responsible for its activities |
A government laboratory is, by default, a legal entity
|
| |
5.2
|
Laboratory director
|
|
|
|
5.2.1
|
Laboratory director competence
|
|
| 30 |
5.2.1 |
Ensure that the laboratory is directed by a person with the specified qualifications |
And the skills and resources required to meet the requirements of ISO 15189 (2022 version) |
|
|
|
Laboratory director responsibilities
|
|
| 31 |
5.2.2 |
Ensure that the laboratory director is responsible for implementing the management system and managing risks associated with all laboratory activities |
In order to identify and address risks associated with patient care and to seize opportunities for improvement. The director of the medical biology laboratory (MBL) is the biologist in charge. The director of the pathology and cytology unit (PCU) is the pathologist in charge |
| 32 |
5.2.2 |
Document the duties and responsibilities of the laboratory director |
Job description available internally, cf. § 8.4 |
|
|
5.2.3
|
Delegation of duties
|
|
| 33 |
5.2.3 |
Document cases where the laboratory director delegates tasks or responsibilities |
To qualified and competent personnel, cf. § 8.4 |
| 34 |
5.2.3 |
Ensure that ultimate responsibility remains with the laboratory director |
Regarding the general operation of the laboratory |
|
|
5.3
|
Laboratory activities
|
|
| |
5.3.1
|
General
|
|
| 35 |
5.3.1 |
Specify and document the scope of the laboratory's activities |
Including activities performed at other sites (point-of-care medical biology testing), in compliance with the requirements of ISO 15189 (2022 version)., cf. § 8.4 |
| 36 |
5.3.1 |
Declare conformity with ISO 15189 requirements solely for the laboratory's activities |
Which excudes externally provided laboratory activities, cf. § 6.8 |
|
|
5.3.2
|
Conformance with requirements
|
|
| 37 |
5.3.2 |
Carry out all laboratory activities in a manner that meets the requirements of ISO 15189 (2022 version) |
And also users, regulatory authorities, and accreditation bodies, cf. § 8.4 |
| |
5.3.3
|
Advisory activities
|
|
| 38 |
5.3.3 |
Ensure that appropriate advisory and interpretation services are available |
And meet the needs of patients and users. Responsibility of the laboratory director, cf. § 8.4.1 |
| 39 |
5.3.3 a |
Establish communication arrangements with laboratory users |
Regarding advice on the selection and use of tests, the type of samples required, the clinical indications and limitations of examination methods, and the frequency of examination requests |
| 40 |
5.3.3 b |
Establish communication arrangements with laboratory users |
In order to provide professional opinions on the interpretation of examination results |
| 41 |
5.3.3 c |
Establish communication arrangements with laboratory users |
In order to facilitate the effective use of laboratory examinations, cf. § 8.4 |
| 42 |
5.3.3 d |
Establish communication arrangements with laboratory users |
Regarding advice in scientific and logistical areas (such as cases where samples do not meet acceptance criteria) |
| |
5.4
|
Structure and authority
|
|
| |
5.4.1
|
General
|
|
| 43 |
5.4.1 a |
Define its organization and structure |
Including its position within the parent organization and the relationships between top management and the technical and support departments (organizational chart), cf. § 8.4 |
| 44 |
5.4.1 b |
Specify the responsibilities and authority of the persons who manage, perform, and verify the work |
That impact the laboratory's activities. Do not overlook communication channels and interpersonal relationships (job descriptions) |
| 45 |
5.4.1 c |
Specify the procedures in sufficient detail |
In order to ensure the long-term conduct of the laboratory's activities and the validity of the results, cf. § 7.3.3 |
| |
5.4.2
|
Quality management
|
|
| 46 |
5.4.2 a |
Ensure that laboratory personnel have the authority and resources to carry out their duties regarding |
Implementation, maintenance and improvement of the management system (job description) |
| 47 |
5.4.2 b |
Ensure that laboratory personnel have the authority and resources to carry out their duties regarding |
Identification of deviations from the management system and realization procedures |
| 48 |
5.4.2 c |
Ensure that laboratory personnel have the authority and resources to carry out their duties regarding |
Initiation of actions to prevent or minimize deviations |
| 49 |
5.4.2 d |
Ensure that laboratory personnel have the authority and resources to carry out their duties regarding |
Reporting to top management on the performance of the management system and any need for improvement, cf. §§ 8.6 and 8.9 |
| 50 |
5.4.2 e |
'Ensure that laboratory personnel have the authority and resources to carry out their duties regarding |
Ensuring the effectiveness of laboratory activities |
| |
5.5
|
Objectives and policies
|
|
| 51 |
5.5 a 1 |
Establish and maintain objectives and policies |
In order to meet the needs and requirements of patients and users, cf. § 8.2.3. Responsibility of the laboratory director. The objectives and policies are also presented in § 8.2.1 |
| 52 |
5.5 a 2 |
Establish and maintain objectives and policies |
In order to commit to good professional practice. Responsibility of the laboratory director |
| 53 |
5.5 a 3 |
Establish and maintain objectives and policies |
In order to provide examinations that fulfil their intended use. Responsibility of the laboratory director |
| 54 |
5.5 a 4 |
Establish and maintain objectives and policies |
In order to comply with the requirements of ISO 15189 (2022 version) |
| |
5.5 b |
Establish and maintain objectives and policies |
In order to ensure that the objectives are measurables and consistent with policies |
| 56 |
5.5 b |
Establish and maintain objectives and policies |
In order to ensure that the objectives and policies are implemented at all levels |
| 57 |
5.5 c |
Establish and maintain objectives and policies |
In order to ensure that when changes to the management system are planned and implemented, the integrity of the management system is maintained. Responsibility of the laboratory director |
| 58 |
5.5 d |
Establish and maintain objectives and policies |
In order to define quality indicators to evaluate and monitor performance through key aspects of pre-examination, examination and post-examination processes in relation to objectives, cf. §§ 8.8.2 and 8.4.2 |
|
|
|
Risk management
|
|
| 59 |
5.6 a |
Establish, implement and maintain processes |
In order to identify risks of harm to patients and improvement opportunities to seize, cf. §§ 7.1, 8.2.4 and 8.5.1. Responsibility of the laboratory director. ISO 22367 provides further details on risks, and ISO 35001 covers biorisk management in medical laboratories |
| 60 |
5.6 a |
Develop actions to address risks |
And opportunities for improvement, cf. § 8.5. Responsibility of the laboratory director |
| 61 |
5.6 b |
Ensure that process effectiveness is evaluated |
And that processes are modified if they are ineffective. Responsibility of the laboratory director, cf. § 8.2.4 |
|
|
6
|
Resources requirements
|
|
|
|
6.1
|
General
|
|
| 62 |
6.1 |
Have available personnel, facilities, equipment, reagents, consumables, and support services |
Essential for managing laboratory activities. Applicable regulations regarding health and safety |
|
|
6.2
|
Personnel
|
|
|
|
6.2.1
|
General
|
|
| 63 |
6.2.1 a
|
Have access to a sufficient number of competent persons |
In order to carry out the laboratory activities |
| 64 |
6.2.1 b |
Act impartially and ethically, be competent, and meet the requirements of the laboratory management system |
This applies to internal and external laboratory personnel who could influence the laboratory's activities. ISO/TS 22583 provides recommendations on point-of-care medical testing |
| 65 |
6.2.1 c |
Communicate to laboratory personnel the importance of meeting the needs and requirements of users |
And requirements of ISO 15189 version 2022 |
| 66 |
6.2.1 d |
Have an onboarding program for new hires |
In order to present them with the general conditions, the premises, the health and safety requirements at work, and the welcome booklet, cf. § 8.4 |
|
|
6.2.2
|
Competence requirements
|
|
| 67 |
6.2.2 a |
Specify the competencies for each role that influences the results of the laboratory's activities |
In terms of level of education, qualifications, training, professional re-training, technical knowledge, know-how, and experience; job descriptions, cf. § 8.4 |
| 68 |
6.2.2 b |
Ensure that personnel possess the necessary skills |
In order to carry out the activities of the laboratory for which they are responsible (medical biologists and medical specialists qualified in anatomical pathology) |
| 69 |
6.2.2 c |
Have a process "Manage personnel" |
Which includes the frequency of competence assessment; see §§ 6.2.2 and 8.2.4. Examples of assessment methods:
- observation of an activity
- review of records
- problem-solving ability
- analysis of aliquots
|
| 70 |
6.2.2 d |
Retain available documents on competence of personnel |
Cf. §§ 6.2.5 and 8.4 |
|
|
6.2.3
|
Authorization
|
|
| 71 |
6.2.3 a |
Authorize personnel to perform specific activities |
Such as select, develop, modify, validate and verify methods |
| 72 |
6.2.3 b |
Authorize personnel to perform specific activities |
Such as review, release and reporting of results |
| 73 |
6.2.3 c |
Authorize personnel to perform specific activities |
Such as use of information systems, including access to patient data, data entry, and examination results |
|
|
6.2.4
|
Continuing education and professional development
|
|
| 74 |
6.2.4 |
Propose a continuing education program |
To personnel who participate in managerial and technical processes, cf. § 8.4 |
| 75 |
6.2.4 |
Ensure that all personnel undergo continuing education |
And programs of professional development |
| 76 |
6.2.4 |
Review regularly the effectiveness of training programs |
And other activities |
| |
6.2.5
|
Personnel records
|
|
| 77 |
6.2.5 a |
Maintain up-to-date procedures and keep records |
Regarding the definition of personnel competency requirements, cf. §§ 6.2.2 a, 8.3.1 and 8.4.1 |
| 78 |
6.2.5 b |
Maintain up-to-date procedures and keep records |
Regarding job descriptions, cf. § 6.2.2 a |
| 79 |
6.2.5 c |
Maintain up-to-date procedures and keep records |
Regarding training and re-training, cf. § 6.2.4 |
| 80 |
6.2.5 d |
Maintain up-to-date procedures and keep records |
Regarding authorization of personnel, cf. § 6.2.3 |
| 81 |
6.2.5 e |
Maintain up-to-date procedures and keep records |
Regarding monitoring competence of personnel, cf. § 6.2.2 |
|
|
6.3
|
Facilities and environmental conditions
|
|
|
|
6.3.1
|
General
|
|
| 82 |
6.3.1 |
Adapt facilities and environmental conditions to laboratory activities |
Cf. § 5.3. ISO 15190 presents details for facilities and environmental conditions |
| 83 |
6.3.1 |
Do not compromise the validity of results or the safety of patients, users, or visitors |
By adapting facilities and environmental conditions to laboratory activities. Examples of detrimental environmental conditions:
- contamination
- dust particles
- electromagnetic interference
- humidity
- temperature
- noise
- vibrations
|
| 84 |
6.3.1 |
Apply these requirements to facilities associated with pre-examination processes |
And to other point-of-care medical biology testing sites and examinations (POCT), cf. Annex A |
| 85 |
6.3.1 |
Specify, monitor, and record requirements regarding facilities and environmental conditions. |
In order to realize laboratory activities, cf. § 8.4 |
|
|
6.3.2
|
Facility controls
|
|
| 86 |
6.3.2 |
Implement, record, monitor and periodically review facilities |
In order to control facilities (risks affecting the validity of the results) |
| 87 |
6.3.2 a |
Include in these facility controls |
Control of access to facilities, including the security, confidentiality, quality and protection of medical information and patient samples |
| 88 |
6.3.2 b |
Include in these facility controls |
For storage facilities, the prevention of contamination, interference, and other factors detrimental to laboratory activities - such as those arising from sources of:
- energy
- lighting
- ventilation
- noise
- water supply
- waste disposal
|
| 89 |
6.3.2 c |
Include in these facility controls |
Prevention of cross-contamination, such as when:
- analysis procedures pose a risk
- work is compromised by an insufficient level of separation
|
| 90 |
6.3.2 d |
Include in these facility controls |
Provision of safety installations and equipment and regular verification of their proper functioning (emergency systems, alarms, access to emergency showers, eyewash equipment, resuscitation equipment) |
| 91 |
6.3.2 e |
Include in these facility controls |
Maintenance of facilities in reliable conditions |
|
|
6.3.3
|
Storage facilities
|
|
| 92 |
6.3.3 a |
Adapt storage space and conditions |
In order to ensure the ongoing integrity of samples, equipment, reagents, consumables and documentation |
| 93 |
6.3.3 b |
Store patient samples and materials used in examination processes in a manner that prevents cross-contamination |
And any deterioration (good clinical and laboratory practices in medically assisted reproduction) |
| 94 |
6.3.3 c |
Ensure that storage and disposal facilities for hazardous materials and biological waste are appropriate for the hazard class of the materials |
In the context of any statutory or regulatory requirements |
|
|
6.3.4
|
Personnel facilities
|
|
| 95 |
6.3.4 |
Ensures that staff have access to toilets, a source of drinking water
|
And facilities for storing personal protective equipment and clothing |
| 96 |
6.3.4 |
Provide space for personnel activities |
And a study (or meeting) and rest area |
|
|
6.3.5
|
Sample collection facilities
|
|
| 97 |
6.3.5 a |
Ensure that sample collection facilities |
Enable for sample collection in a manner that does not invalidate the results or compromise the quality of the examinations. ISO 20658 provides details regarding sample collection facilities |
| 98 |
6.3.5 b |
Ensure that sample collection facilities |
Ensure patient confidentiality, comfort, and the meeting of their needs, as well as the reception of accompanying persons |
| 99 |
6.3.5 c |
Ensure that sample collection facilities |
Feature two separate areas for patient reception and sample collection |
| 100 |
6.3.5 d |
Ensure that sample collection facilities |
Have functional first-aid equipment available for patients and personnel |
|
|
6.4
|
Equipment
|
|
|
|
6.4.1
|
General
|
|
| 101 |
6.4.1 |
Have a process "Manage equipment" |
In order to ensure proper functioning and prevent any contamination or deterioration. Equipment management encompasses the selection, acquisition, installation, acceptance testing, handling, transport, storage, use, maintenance, and decommissioning of equipment. Examples of equipment include instruments (hardware and software), as well as measurement, information, storage, and transport systems, cf. § 8.2.4 |
|
|
6.4.2
|
Equipment requirements
|
|
| 102 |
6.4.2 a |
Have access to equipment |
In order to properly carry out the laboratory activities |
| 103 |
6.4.2 b |
Ensure that the requirements of ISO 15189 version 2022 are met |
When equipment is used without direct laboratory supervision or without adhering to all manufacturer specifications |
| 104 |
6.4.2 c |
Identify each piece of equipment uniquely |
And retain an equipment register, cf. §§ 6.4.7 and 8.4 |
| 105 |
6.4.2 d |
Maintain regularly the equipment |
And replace equipment in order to ensure the quality of examination results |
| |
6.4.3
|
Equipment acceptance procedure
|
|
| 106 |
6.4.3 |
Verify that the equipment complies with the acceptance criteria |
Before being placed into service |
| 107 |
6.4.3 |
Enable the achievement of measurement accuracy or measurement uncertainty in order to provide a valid result |
According to §§ 7.3.3 and 7.3.4. Verification of equipment acceptance tests may be based on the equipment's calibration certificate following its return to service |
| |
6.4.4
|
Equipment instructions for use
|
|
| 108 |
6.4.4 a |
Apply appropriate safeguards |
In order to avoid any equipment unintended adjustments that could invalidate examination results |
| 109 |
6.4.4 b |
Ensure that equipment is used by trained personnel |
Possessing the required authority and competence |
| 110 |
6.4.4 c |
Ensure that equipment operating instructions are available |
To anyone authorized to use the equipment |
| 111 |
6.4.4 d |
Use the equipment according to the manufacturer's specifications |
Unless a new use has been authorized by the laboratory |
| |
6.4.5
|
Equipment maintenance and repair
|
|
| 112 |
6.4.5 a |
Establish and implement an equipment preventive maintenance program |
In accordance with the manufacturer's instructions |
| 113 |
6.4.5 a |
Record deviations from manufacturer's schedules |
Or regarding manufacturer's instructions, cf. § 8.4 |
| 114 |
6.4.5 b |
Maintain equipment in a safe working condition |
In order to ensure there is no health risk |
| 115 |
6.4.5 b |
Include electrical safety and emergency stops in equipment maintenance requirements |
As well as the safe handling and disposal of hazardous materials by authorized personnel |
| 116 |
6.4.5 c |
Take defective equipment out of service |
Or equipment that does not meet specified requirements |
| 117 |
6.4.5 c |
Identify out-of-service equipment until its proper operation has been demonstrated |
By means of a label or marking |
| 118 |
6.4.5 c |
Examine the effect of the defect or deviation |
From specified requirements |
| 119 |
6.4.5 c |
Implement corrective actions for noncompliant work |
Cf. § 7.5 |
| 120 |
6.4.5 d |
Decontaminate the equipment in a suitable location, if necessary, before use, repair, or decommissioning |
And provide the necessary personal protective equipment |
| |
6.4.6
|
Equipment adverse incident reporting
|
|
| 121 |
6.4.6 |
Investigate adverse events and incidents involving specific equipment |
And report them to the manufacturer, supplier, and the competent authorities, as appropriate (reagent vigilance and medical device vigilance), cf. § 8.4 |
| 122 |
6.4.6 |
Have procedures in place to respond to a manufacturer recall or other notice |
And implement the actions required by the manufacturer, cf. § 8.3.1 |
| |
6.4.7
|
Equipment records
|
|
| 123 |
6.4.7 |
Retain records for each item of equipment |
That can influence the results of laboratory activities, cf. § 8.4 |
| 124 |
6.4.7 a |
Include in these records |
Detailed information on the manufacturer, the supplier, the equipment components, and the proprietary software |
| 125 |
6.4.7 b |
Include in these records |
Dates of receipt, acceptance testing and entering into service |
| 126 |
6.4.7 c |
Include in these records |
Evidence that equipment conforms with acceptability criteria |
| 127 |
6.4.7 d |
Include in these records |
Location of equipment |
| 128 |
6.4.7 e |
Include in these records |
Condition when received (new, used, reconditioned) |
| 129 |
6.4.7 f |
Include in these records |
Manufacturer's instructions |
| 130 |
6.4.7 g |
Include in these records |
Preventive maintenance program |
| 131 |
6.4.7 h |
Include in these records |
Maintenance activities performed (internally and by the approved external service provider) |
| 132 |
6.4.7 i |
Include in these records |
Any damage, malfunction, modification or repair |
| 133 |
6.4.7 j |
Include in these records |
Dated performance results (reports, calibration or verification certificates) |
| 134 |
6.4.7 k |
Include in these records |
Status of the equipment (active, out-of-service, quarantined, obsolete) |
| 135 |
6.4.7 |
Maintain the records and have them readily available |
For the lifespan of the equipment plus an additional 24 months, cf. § 8.4.3 |
| |
6.5
|
Equipment calibration and metrological traceability
|
|
| |
6.5.1
|
General
|
|
| 136 |
6.5.1 |
Specify calibration and traceability requirements |
Sufficient to ensure consistent examination results |
| 137 |
6.5.1 |
Include calibration and metrological traceability requirements |
Regarding quantitative analyte measurement methods |
| 138 |
6.5.1 |
Specify the characteristic being evaluated and the requirements for reproducibility over time |
Regarding qualitative and semi-qualitative methods. Examples of methods that do not allow for metrological traceability:
- detection of anti-erythrocyte antibodies
- assessment of antibiotic susceptibility
- genetic testing
- erythrocyte sedimentation rate
- flow cytometry marker staining
- HER2 immunohistochemical staining of tumors
|
| |
6.5.2
|
Equipment calibration
|
|
| 139 |
6.5.2 |
Maintain procedures for the calibration of equipment |
That directly or indirectly affects examination results, cf. § 8.3.1 |
| 140 |
6.5.2 a |
Include in the procedures |
Conditions of use and manufacturer's instructions for calibration |
| 141 |
6.5.2 b |
Include in the procedures |
Results of the metrological traceability, cf. § 8.4 |
| 142 |
6.5.2 c |
Include in the procedures |
Verification of:
- the requiredmeasurement accuracy
- the functioning of the measurement system at specified intervals
|
| 143 |
6.5.2 d |
Include in the procedures |
Calibration status and date of re-calibration |
| 144 |
6.5.2 e |
Include in the procedures |
Retention of provision updates when using correction factors for recalibration |
| 145 |
6.5.2 f |
Include in the procedures |
Handling of situations where calibration was out of limits, in order to reduce risks to laboratory operations and patients |
| |
6.5.3
|
Metrological traceability of measurement results
|
|
| 146 |
6.5.3 a |
Establish and maintain the metrological traceability of measurement results |
By means of an unbroken and documented chain of calibrations, linking the results to an appropriate reference. Traceability information may be provided by a manufacturer of examination systems |
| 147 |
6.5.3 b |
Ensure that measurement results are traceable, including to the International System of Units (SI) |
Through calibration performed by a competent laboratory (ISO 17025 accredited) |
| 148 |
6.5.3 b |
Ensure that measurement results are traceable, including to the International System of Units (SI) |
Using certified values of reference materials provided by a competent producer (certified to ISO 17034 or ISO 15194) |
| 149 |
6.5.3 c |
Apply other means of demonstrating the reliability of results |
Such as results from reference measurement procedures, specified methods, or consensus standards, through an appropriate comparison, cf. § 8.3.1 |
| 150 |
6.5.3 c |
Apply other means of demonstrating the reliability of results |
As the measurement of the reference material according to a specific procedure. ISO 17511 provides information on how to manage the trade-offs regarding the metrological traceability of measurands |
| 151 |
6.5.3 d |
Establish traceability to reference genetic sequences |
For all genetic examinations |
| 152 |
6.5.3 e |
Demonstrating traceability for qualitative methods |
By examining a known material or a sufficient number of previously analyzed samples to demonstrate consistent identification and, where necessary, the intensity of the reaction |
| |
6.6
|
Reagent and consumables
|
|
| |
6.6.1
|
General
|
|
| 153 |
6.6.1 |
Have processes in place for the selection, procurement, receipt, storage, and acceptance testing of reagents and consumables |
Including inventory management. CE marking (guaranteeing conformity with requirements), cf. § 8.2.4 |
| |
6.6.2
|
Reagent and consumables - Receipt and storage
|
|
| 154 |
6.6.2 |
Store reagents and consumables according to the manufacturer's specifications |
And monitor environmental conditions, if necessary |
| 155 |
6.6.2 |
Verify that the receiving location has adequate capacity |
In order to prevent any damage or deterioration when the laboratory does not receive the reagents and consumables directly |
| |
6.6.3
|
Reagent and consumables - Acceptance testing
|
|
| 156 |
6.6.3 |
Verify the performance of each reagent, new reagent kit formulation, or new manufacturing lot prior to use or the release of results |
Refer to § 7.3.7.2 regarding the comparison between the new and old lot as evidence of acceptance. Reagent and Consumable Management Procedure, cf. § 8.3.1 |
| 157 |
6.6.3 |
Verify the performance of consumables that may affect the quality of examinations |
Before use. Verification may be based on the reagent's certificate of analysis |
| |
6.6.4
|
Reagent and consumables - Inventory management
|
|
| 158 |
6.6.4 |
Establish a management system for reagent |
And consumable stocks, cf. § 8.4 |
| 159 |
6.6.4
|
Distinguish between reagents and consumables accepted for use |
And those that have not been inspected and accepted for use, cf. § 8.4 |
| |
6.6.5
|
Reagent and consumables - Instructions for use
|
|
| 160 |
6.6.5 |
Ensure that reagent instructions for use are easily accessible |
Including for consumables |
| 161 |
6.6.5 |
Use reagents and consumables in accordance with the manufacturer's specifications |
If they are to be used for other applications, the examination methods must undergo validation, cf. § 7.7.3 |
| |
6.6.6
|
Reagent and consumables - Adverse incident reporting
|
|
| 162 |
6.6.6 |
Investigate adverse events and incidents caused by specific reagents or consumables |
And report them to the manufacturer, supplier, and regulatory authorities, if necessary |
| 163 |
6.6.6 |
Have a procedure in place to respond to a manufacturer recall or other notice |
And implement the actions recommended by the manufacturer, cf. § 8.3.1 |
| |
6.6.7
|
Reagent and consumables - Records
|
|
| 164 |
6.6.7 |
Maintain records for each reagent and consumable |
Regarding the performance of examinations, cf. § 8.4 |
| 165 |
6.6.7 a |
Include in these records |
Identity of the reagent or consumable |
| 166 |
6.6.7 b |
Include in these records |
Manufacturer's instructions, name and batch code or lot number |
| 167 |
6.6.7 c |
Include in these records |
The date of receipt, condition upon receipt, expiry date, date of first use, and, if applicable, the date the reagent or consumable was taken out of service |
| 168 |
6.6.7 d |
Include in these records |
Initial and current suitability for use of the reagent or consumable |
| 169 |
6.6.7 |
Include in these records when reagents are prepared or combined in-house |
And in addition, the personnel involved in the preparation, as well as the preparation and expiry dates |
| |
6.7
|
Service agreements
|
|
| |
6.7.1
|
Agreements with laboratory users
|
|
| 170 |
6.7.1 |
Have a procedure to establish and review agreements |
Concerning laboratory activities, cf. § 8.3.1 |
| 171 |
6.7.1 a |
Ensure that the procedure includes |
Adequately specified requirements |
| 172 |
6.7.1 b |
Ensure that the procedure includes |
Capability and resources to meet the requirements |
| 173 |
6.7.1 c |
Ensure that the procedure includes |
Notification to the user of specific activities that will be transmitted to other laboratories or consultants |
| 174 |
6.7.1 |
Inform users of any changes to the contract |
That could impact examination results |
| 175 |
6.7.1 |
Retain records of reviews, including any significant changes |
Cf. § 8.4 |
| |
6.7.2
|
Agreements with POCT operators
|
|
| 176 |
6.7.2 |
Ensure that responsibilities and authorities are specified |
And communicated regarding contracts between the laboratory and other parties using point-of-care testing (POCT) services, cf. Annex A.2 |
| |
6.8
|
Externally provided products and services
|
|
| |
6.8.1
|
General
|
|
| 177 |
6.8.1 a |
Ensure that products and services provided by external providers, which impact the laboratory's activities, are appropriate |
And are intended to be integrated into the laboratory's activities. Examples of services:
- sample collection
- pipette calibration
- equipment maintenance
- external quality assessment programs
|
| 178 |
6.8.1 b |
Ensure that products and services provided by external providers, which impact the laboratory's activities, are appropriate |
When they are provided directly to the user |
| 179 |
6.8.1 c |
Ensure that products and services provided by external providers, which impact the laboratory's activities, are suitable |
And used to contribute to the proper functioning of the laboratory |
| 180 |
6.8.1 |
Collaborate with other organizational departments or functions |
In order to meet the requirement regarding products and services provided by external providers |
| |
6.8.2
|
Referral laboratories and consultants
|
|
| 181 |
6.8.2 a |
Communicate requirements to subcontracting laboratories and consultants providing interpretations and consulting services |
Regarding procedures, analyses, reports, and consulting services |
| 182 |
6.8.2 b |
Communicate requirements to subcontracting laboratories and consultants providing interpretations and consulting services |
Regarding management of critical results |
| 183 |
6.8.2 c |
Communicate requirements to subcontracting laboratories and consultants providing interpretations and consulting services |
Regarding personnel qualifications and demonstration of competence |
| 184 |
6.8.2 |
Ensure that examination results provided by the subcontracting laboratory are communicated to the person making the request |
Responsibility of the referring laboratory, unless otherwise specified in the contract |
| 185 |
6.8.2 |
Maintain the list of referral laboratories and consultants up-to-date |
Cf. § 8.4 |
| |
6.8.3
|
Review and approval of externally provided products and services
|
|
| 186 |
6.8.3 a |
Maintain procedures and keep records regarding |
Definition, review, and approval of laboratory requirements for all externally provided products and services, cf. §§ 8.3.1 and 8.4 |
| 187 |
6.8.3 b |
Maintain procedures and keep records regarding |
Defining criteria for the qualification, selection, performance evaluation, and re-evaluation of external service providers. The laboratory complies with the requirements of ISO 15189 (2022 version) |
| 188 |
6.8.3 c |
Maintain procedures and keep records regarding |
Referral of samples |
| 189 |
6.8.3 d |
Maintain procedures and keep records regarding |
That externally provided products and services comply with the laboratory's requirements or the requirements of ISO 15189 (2022 version) prior to use |
| 190 |
6.8.3 e |
Maintain procedures and keep records regarding |
The implementation of actions following the performance evaluation of external providers |
|
|
7
|
Process requirements
|
|
|
|
7.1
|
General
|
|
|
191
|
7.1
|
Identify risks associated with patient care |
Within pre-examination, examination, and post-examination processes |
|
192
|
7.1
|
Assess risks |
And mitigate them to the extent possible |
|
193
|
7.1
|
Communicate the residual risk to users |
As appropriate |
|
194
|
7.1
|
Monitor and evaluate identified risks and the effectiveness of the processes for managing them |
Based on the potential harm to the patient |
|
195
|
7.1
|
Identify opportunities to improve patient care |
And develop a framework to seize these opportunities, cf. § 8.5 |
|
|
7.2
|
Pre-examination processes
|
|
|
|
7.2.1
|
General
|
|
| 196 |
7.2.1 |
Have procedures for pre-examination activities |
And make these procedures available to the relevant personnel; see § § 8.3.1. ISO 20658 provides information on sample collection and transport. ISO standards 20186-1 to -3, ISO 20166, ISO 20184, ISO 23118, and ISO 4307 provide information on samples from particular sources for specific analytes
|
| |
7.2.2
|
Laboratory information for patients and users
|
|
| 197 |
7.2.2 |
Make available for users and patients |
Appropriate information |
| 198 |
7.2.2 |
Ensure that the information is sufficiently detailed to provide users with understandable data |
Regarding the scope of the laboratory's activities and its requirements |
| 199 |
7.2.2 a |
Include in the laboratory information |
Address, opening hours, and contact details |
| 200 |
7.2.2 b |
Include in the laboratory information |
Procedures for examination request and collecting samples, cf. § 8.3.1 |
| 201 |
7.2.2 c |
Include in the laboratory information |
The scope of the laboratory's activities and the turnaround time for results. Timeframes defined for urgent tests, cf. § 8.4 |
| 202 |
7.2.2 d |
Include in the laboratory information |
The availability of advisory services |
| 203 |
7.2.2 e |
Include in the laboratory information |
Requirements for patient consent |
| 204 |
7.2.2 f |
Include in the laboratory information |
Known factors affecting the performance of the examination or the interpretation of the results |
| 205 |
7.2.2 g |
Include in the laboratory information |
The process "Manage complaints", cf. § 8.2.4 |
|
|
7.2.3
|
Requests for providing laboratory examinations
|
|
|
|
7.2.3.1
|
General
|
|
| 206 |
7.2.3.1 a |
Treat each examination request as a contract |
Once the request has been accepted by the laboratory |
| 207 |
7.2.3.1 b |
Provide sufficient detail in the examination request |
To ensure unequivocal traceability of the patient in relation to the request and the sample |
| 208 |
7.2.3.1 b |
Provide sufficient detail in the examination request |
Identity and contact information of the requester |
| 209 |
7.2.3.1 b |
Provide sufficient detail in the examination request |
Identification of the requested examinations |
| 210 |
7.2.3.1 b |
Provide sufficient detail in the examination request |
Provision of clinical information, technical advice, and interpretation |
| 211 |
7.2.3.1 c |
Provide information regarding the examination request |
In an appropriate format or medium acceptable to the user |
| 212 |
7.2.3.1 d |
Communicate with the user or their representative |
To clarify their request |
| |
7.2.3.2
|
Oral requests
|
|
| 213 |
7.2.3.2 |
Have a procedure in place for managing oral requests for review |
Including the provision of written confirmation of the request within a specified timeframe., cf. § 8.3.1 |
|
|
7.2.4
|
Primary sample collection and handling
|
|
|
|
7.2.4.1
|
General
|
|
| 214 |
7.2.4.1 |
Have procedures for the collection and handling of primary samples |
Cf. § 8.3.1 |
| 215 |
7.2.4.1 |
Make information available |
To the persons responsible for sample collection |
| 216 |
7.2.4.1 |
Record any deviation from the established collection procedures |
Cf. § 8.4 |
| 217 |
7.2.4.1 |
Assess, record, and communicate to appropriate personnel the risks and impact on patient care |
Regarding the acceptance or rejection of a sample, cf. § 8.4 |
| 218 |
7.2.4.1 |
Review regularly requirements regarding sample volume, collection devices, and stabilizing additives |
In order to ensure that a sufficient sample quantity is collected and that samples are collected correctly to preserve analyte integrity |
| |
7.2.4.2
|
Information for pre-collection activities
|
|
| 219 |
7.2.4.2 |
Provide information and instructions regarding pre-collection activities |
Sufficiently detailed to ensure the integrity of the sample, cf. § 8.4 |
| 220 |
7.2.4.2 a |
Include in the information regarding pre-collection activities |
Patient preparation (instructions for healthcare staff, those performing the sample collection, and the patient) |
| 221 |
7.2.4.2 b |
Include in the information regarding pre-collection activities |
The nature and quantity of the primary sample to be taken, the description of the equipment to be used, any necessary additives and the order of sample collection |
| 222 |
7.2.4.2 c |
Include in the information regarding pre-collection activities |
The precise time at which the collection will be made |
| 223 |
7.2.4.2 d |
Include in the information regarding pre-collection activities |
Communication of relevant clinical information, performance of examinations, or interpretation of results (history of drug administration) |
| 224 |
7.2.4.2 e |
Include in the information regarding pre-collection activities |
Sample labeling (patient and collection site identification) |
| 225 |
7.2.4.2 f |
Include in the information regarding pre-collection activities |
Sample acceptance and rejection criteria |
|
|
7.2.4.3
|
Patient consent
|
|
| 226 |
7.2.4.3 a |
Obtain the consent of the patient |
For all procedures carried out on the patient (consent can be implied), cf. § 8.3.1 |
| 227 |
7.2.4.3 b |
Request a more detailed explanation and, in some cases, a record |
For special procedures that carry a significant risk of complications following the intervention, cf. § 8.4 |
| 228 |
7.2.4.3 c |
Perform the necessary procedures, provided they are in the patient's best interest |
In an emergency, when obtaining the patient's consent is not possible |
|
|
7.2.4.4
|
Instructions for collection activities
|
|
| 229 |
7.2.4.4 a |
Provide instructions for verifying the identity of the patient from whom the primary sample was collected |
In order to ensure that collection and pre-examination storage are performed safely, correctly, and in a clinically appropriate manner |
| 230 |
7.2.4.4 b |
Provide instructions regarding the verification (and, where relevant, the record) of patient compliance with pre-examination requirements (fasting status, timing of last medication dose) |
In order to ensure that sample collection and pre-examination storage are carried out safely, correctly, and in a clinically appropriate manner, cf. § 8.4 |
| 231 |
7.2.4.4 c |
Provide instructions regarding primary sample collection (description of equipment used, necessary additives, order of sample collection) |
In order to ensure that sample collection and pre-examination storage are carried out safely, correctly, and in a clinically appropriate manner |
| 232 |
7.2.4.4 d |
Provide instructions regarding the labeling of primary samples (unequivocal link to the patient) |
In order to ensure that sample collection and pre-examination storage are carried out safely, correctly, and in a clinically appropriate manner |
| 233 |
7.2.4.4 e |
Provide instructions regarding the record of the person collecting the primary sample, the date, and, where relevant, the time of collection |
In order to ensure that sample collection and pre-examination storage are carried out safely, correctly, and in a clinically appropriate manner |
| 234 |
7.2.4.4 f |
Provide instructions regarding separation requirements or the aliquoting of the primary sample |
In order to ensure that sample collection and pre-examination storage are carried out safely, correctly, and in a clinically appropriate manner |
| 235 |
7.2.4.4 g |
Provide instructions regarding sample storage conditions prior to transfer |
In order to ensure that sample collection and pre-examination storage are carried out safely, correctly, and in a clinically appropriate manner |
| 236 |
7.2.4.4 h |
Provide instructions regarding the safe disposal of used materials |
In order to ensure that sample collection and pre-examination storage are carried out safely, correctly, and in a clinically appropriate manner |
| |
7.2.5
|
Sample transportation
|
|
| 237 |
7.2.5 a 1 |
Provide instructions for sample packaging for transport |
In order to ensure the safe and timely transport of samples |
| 238 |
7.2.5 a 2 |
Provide instructions to ensure an appropriate timeframe between sample collection and receipt at the laboratory |
Into ensure safe and timely sample transport. order to ensure the safe and timely transport of samples |
| 239 |
7.2.5 a 3 |
Provide instructions for maintaining the required temperature range (during collection and handling) |
In order to ensure safe and timely sample transport |
| 240 |
7.2.5 a 4 |
Provide instructions for compliance with any specific requirements to ensure sample integrity (use of stabilizing additives) |
In order to ensure the safe and timely transport of samples |
| 241 |
7.2.5 b |
Immediately notify the organization responsible for transport |
When sample integrity is compromised or in the event of a health risk |
| 242 |
7.2.5 b |
Take measures to reduce the risk and prevent recurrence |
When sample integrity is compromised or in the event of a health risk |
| 243 |
7.2.5 c |
Establish and periodically evaluate adequacy of sample transportation systems |
Cf. § 8.4 |
|
|
7.2.6
|
Sample receipt
|
|
| |
7.2.6.1
|
Sample receipt procedure
|
|
| 244 |
7.2.6.1 a |
Include in the sample receipt procedure |
Traceability of samples (request, labeling, patient and anatomical site, when applicable), cf. § 8.3.1 |
| 245 |
7.2.6.1 b |
Include in the sample receipt procedure |
Criteria for acceptance and rejection of samples |
| 246 |
7.2.6.1 c |
Include in the sample receipt procedure |
Recording the date (and time, if relevant) of sample receipt |
| 247 |
7.2.6.1 d |
Include in the sample receipt procedure |
The person receiving the sample (where applicable) |
| 248 |
7.2.6.1 e |
Include in the sample receipt procedure |
Evaluation of samples by authorized personnel (to ensure their compliance with acceptance criteria) |
| 249 |
7.2.6.1 f |
Include in the sample receipt procedure |
Instructions for urgent samples (specific labeling, transport, handling of urgent cases, turnaround times, specific reporting criteria), cf. § 8.3 |
| 250 |
7.2.6.1 g |
Include in the sample receipt procedure |
The guarantee that all sample aliquots are traceable to the original sample |
|
|
7.2.6.2
|
Sample acceptance exceptions
|
|
| 251 |
7.2.6.2 a 1 |
Use processes to ensure best interests of the patient in the event of a noncompliant sample |
Due to incorrect identification (of the patient or the sample)., cf. § 8.2.4 |
| 252 |
7.2.6.2 a 2 |
Use processes to ensure best interests of the patient in the event of a noncompliant sample |
Due to sample instability (delay in transport), cf. § 8.2.4 |
| 253 |
7.2.6.2 a 3 |
Use processes to ensure best interests of the patient in the event of a noncompliant sample |
Due to incorrect sample temperature (storage or handling), cf. § 8.2.4 |
| 254 |
7.2.6.2 a 4 |
Use processes to ensure best interests of the patient in the event of a noncompliant sample |
Due to the use of inappropriate sample collection equipment, cf. § 8.2.4 |
| 255 |
7.2.6.2 a 5 |
Use processes to ensure best interests of the patient in the event of a noncompliant sample |
Due to insufficient sample volume, cf. § 8.2.4 |
| 256 |
7.2.6.2 b |
Following an assessment of the risk to patient safety, indicate the nature of the anomaly in the report when accepting a sample with clinically significant alteration or an irreplaceable sample |
And, where appropriate, advise caution regarding the interpretation of the results |
|
|
7.2.7
|
Pre-examination handling, preparation and storage
|
|
| |
7.2.7.1
|
Sample protection
|
|
| 257 |
7.2.7.1 |
Establish procedures and have appropriate facilities in place to secure patient samples, ensure sample integrity |
And prevent any loss or degradation during handling, preparation, and storage, cf. § 8.3.1 |
| |
7.2.7.2
|
Criteria for additional examination requests
|
|
| 258 |
7.2.7.2 |
Include in the laboratory procedures acceptable time limits |
For requesting additional examinations on the same sample, cf. § 8.3.1 |
|
|
7.2.7.3
|
Sample stability
|
|
| 259 |
7.2.7.3 |
Specify and monitor, where relevant, the time interval between sample collection, processing, and analysis |
Taking into account the stability of the analyte in the primary sample |
|
|
7.3
|
Examination processes
|
|
|
|
7.3.1
|
General
|
|
|
260
|
7.3.1 a
|
Select and use validated analyte methods |
In order to ensure the clinical use of examination results |
| 261 |
7.3.1 b |
Base the performance specifications for each analyte method on the intended use of the test |
And its impact on patient management |
| 262 |
7.3.1 c |
Keep procedures and associated documentation up to date and ensure their availability to staff |
Regarding all laboratory activities, cf. § 8.3.1 |
| 263 |
7.3.1 d |
Follow established procedures |
Cf. § 8.3.1 |
| 264 |
7.3.1 d |
Record personnel involved in examination processes |
Including POCT operators, cf. § 8.4 |
| 265 |
7.3.1 e |
Evaluate regularly examination methods performed by authorized personnel |
In order to ensure they are clinically appropriate for the requests received |
| |
7.3.2
|
Verification of examination methods
|
|
|
266
|
7.3.2 a
|
Have a procedure in place to verify that the laboratory can correctly implement examination methods before using them for the first time |
By ensuring that the required performance levels (specified by the manufacturer or expected for the method) will be achieved, cf. § 8.3.1 |
| 267 |
7.3.2 b |
Ensure that the confirmed performance verification specifications for the examination method are appropriate for the intended use |
Regarding examination results |
| 268 |
7.3.2 c |
Ensure that the scope of the examination method verification is sufficient |
To guarantee the validity of results and clinical decision-making |
| 269 |
7.3.2 d |
Review the verification results |
And record whether the results meet requirements |
| 270 |
7.3.2 e |
Conduct a new verification as extensive as necessary |
When a method is revised by the issuing body |
| 271 |
7.3.2 f 1 |
Retain records relating to the verification performed |
Including the performance specifications to be met, cf. § 8.4 |
| 272 |
7.3.2 f 2 |
Retain records relating to the verification performed |
Including obtained results, cf. § 8.4 |
| 273 |
7.3.2 f 3 |
Retain records relating to the verification performed |
Including a statement regarding whether performance specifications have been met and, if not, the actions taken, cf. § 8.4 |
| |
7.3.3
|
Validation of examination methods
|
|
|
274
|
7.3.3 a 1
|
Validate examination methods in the case of |
Laboratory designed or developed methods |
| 275 |
7.3.3 a 2 |
Validate examination methods in the case of |
Methods applied outside their intended scope, such as:
- outside the manufacturer's instructions for use
- outside the initially validated measurement range
- adaptation of reagents used with instruments not validated by the supplier
|
| 276 |
7.3.3 a 3 |
Validate examination methods in the case of |
After subsequently modified validated method |
| 277 |
7.3.3 b |
Validate examination methods |
With sufficient extensive scope |
| 278 |
7.3.3 b |
Confirm that the specific requirements for the intended use have been met |
By means of objective evidence (performance specifications) |
| 279 |
7.3.3 b |
Ensure the scope of the examination method validation is sufficient |
To guarantee the validity of results for clinical decision-making |
| 280 |
7.3.3 c |
Review validation results |
By personnel with the appropriate authorization and competence |
| 281 |
7.3.3 c |
Record whether the results meet the specified requirements |
Cf. § 8.4 |
| 282 |
7.3.3 d |
Review the clinical impact |
When changes are proposed to a validated examination method |
| 283 |
7.3.3 d |
Assess the advisability of implementing the modified method |
When changes are proposed to a validated examination method |
| 284 |
7.3.3 e 1 |
Retain records relating to the validation performed |
Including the validation procedure used, cf. § 8.4 |
| 285 |
7.3.3 e 2 |
Retain records relating to the validation performed |
Including specific requirements for the intended use, cf. § 8.4 |
| 286 |
7.3.3 e 3 |
Retain records relating to the validation performed |
Including determination of the performance specifications of the method, cf. § 8.4 |
| 287 |
7.3.3 e 4 |
Retain records relating to the validation performed |
Including results obtained, cf. § 8.4 |
| 288 |
7.3.3 e 5 |
Retain records relating to the validation performed |
Including a statement on the validity of the method, detailing its fitness for the intended use, cf. § 8.4 |
| |
7.3.4
|
Evaluation of measurement uncertainty (MU)
|
|
|
289
|
7.3.4 a
|
Evaluate and maintain measurement uncertainty, where relevant |
Regarding quantitative measured values. Assists in interpreting results (decision threshold level, comparison with previous results) |
| 290 |
7.3.4 a |
Compare and document measurement uncertainty |
Regarding performance specifications, cf. § 8.4. ISO/TS 20914 provides information on MU and examples |
| 291 |
7.3.4 b |
Review regularly evaluations |
Of MU |
| 292 |
7.3.4 c |
Document the justification for not evaluating MU |
Regarding examination procedures for which an MU evaluation is not possible or relevant |
| 293 |
7.3.4 d |
Made available MU information |
To laboratory users on request |
| 294 |
7.3.4 e |
Consider other sources of uncertainty (biological variation) |
When users ask for clarification on the MU |
| 295 |
7.3.4 f |
Estimate the measurement uncertainty of the measurand using representative positive and negative samples |
When the qualitative result of an examination is based on the determination of quantitative data and this result is specified as positive or negative relative to a threshold |
| 296 |
7.3.4 g |
Take into account the intermediate measurement uncertainty or IQC results that yield quantitative data for high-risk process steps |
For examinations involving qualitative results, cf. §§ 7.3.7.2 and § 8.2.4 |
| 297 |
7.3.4 h |
Consider the MU when performing method verification or validation |
When relevant |
|
|
7.3.5
|
Biological reference intervals and clinical decision limits
|
|
|
298
|
7.3.5
|
Define and communicate biological reference intervals and clinical decision limits to users |
When these intervals are necessary for the interpretation of examination results |
| 299 |
7.3.5 a |
Define biological reference intervals |
And clinical decision limits |
| 300 |
7.3.5 a |
Document the basis for establishing the intervals, taking patient risk into account |
In order to reflect the laboratory's patient population. The manufacturer's biological reference values may be used if the reference population for those values is verified and deemed acceptable by the laboratory |
| 301 |
7.3.5 b |
Review periodically biological reference intervals |
And clinical decision limits |
| 302 |
7.3.5 b |
Communicate to users |
Any changes to biological reference intervals and decision limits |
| 303 |
7.3.5 c |
Assess and communicate, where relevant, the impact of changes to an examination or pre-examination method |
On associated biological reference intervals and clinical decision limits |
| 304 |
7.3.5 d |
Identify the characteristic of the biological reference interval |
For examinations that identify the presence or absence of a characteristic (genetic analyses) |
|
|
7.3.6
|
Documentation of examination procedures
|
|
|
305
|
7.3.6 a
|
Documenting examination procedures in sufficient detail |
To ensure consistent application of activities and the validity of results, cf. § 8.3 |
| 306 |
7.3.6 b |
Draft procedures in a language understood by the staff |
And keep them available on-site, cf. § 8.3.1 |
| 307 |
7.3.6 c |
Cross-reference any document |
To the relevant procedure, cf. § 8.3.1 |
| 308 |
7.3.6 d |
Integrate information from product instruction manuals, including sufficiently detailed guidance |
Into the relevant procedures, cf. § 8.3.1 |
| 309 |
7.3.6 e |
Explain to users the consequences of a validated modification to an examination procedure |
Change that is likely to have an impact on the interpretation of the results |
| 310 |
7.3.6 f |
Master all documents associated with the examination process |
In accordance with the requirements of the sub-clause 8.3 |
|
|
7.3.7
|
Ensuring the validity of examination results
|
|
|
|
7.3.7.1
|
General
|
|
|
311
|
7.3.7.1
|
Have a procedure in place to monitor the validity of results |
Cf. § 8.3.1 |
| 312 |
7.3.7.1 |
Record resulting data in such a way that trends are detectable |
Including shifts indata |
| 313 |
7.3.7.1 |
Apply statistical techniques, where practicable |
In order to review the results |
| 314 |
7.3.7.1 |
Plan monitoring |
And review monitoring |
| |
7.3.7.2
|
Internal quality control (IQC)
|
|
| 315 |
7.3.7.2 a |
Have an internal quality control (IQC) procedure in place |
In order to continually monitor the validity of examination results against specified criteria, verify that the intended quality is achieved, and ensure the validity of results for clinical decision-making, cf. § 8.3.1 |
| 316 |
7.3.7.2 a 1 |
Take into account the intended clinical use of the examination |
As performance specifications for the same measurand may vary depending on the clinical context |
| 317 |
7.3.7.2 a 2 |
Have a procedure that allows for the detection of variations depending on the batches of reagents |
Or standards of the examination method, cf. § 8.3.1 |
| 318 |
7.3.7.2 a 2 |
Have a procedure in place ensuring that a lot change for the internal quality control (IQC) material does not occur on the same day, or within the same run |
As a lot change for reagents or calibrators, cf. § 8.3.1 |
| 319 |
7.3.7.2 a 3 |
Consider using third-party IQC material (instrument or reagent manufacturer) |
Either instead of or in addition to control material supplied by the manufacturer |
| 320 |
7.3.7.2 b |
Select IQC material |
Adapted for its intended purpose |
| 321 |
7.3.7.2 b 1 |
Include in the factors to be considered |
Stability for the intended purpose |
| 322 |
7.3.7.2 b 2 |
Include in the factors to be considered |
The nature of the matrix, as close as possible to the patient samples |
| 323 |
7.3.7.2 b 3 |
Include in the factors to be considered |
The behavior of the IQC material with respect to the examination method, as close as possible to patient samples |
| 324 |
7.3.7.2 b 4 |
Include in the factors to be considered |
Selection of an IQC material suitable for clinical use, with concentrations at or near clinical decision limits and, if possible, within the measurement range of the examination method |
| 325 |
7.3.7.2 c |
Consider the use of other methods for IQC |
When appropriate IQC material is not available |
| 326 |
7.3.7.2 c 1 |
Use other methods |
Such as an analysis of patient result drift (moving average applied to results, or a percentage of samples falling below or above a given value or associated with a diagnosis) |
| 327 |
7.3.7.2 c 2 |
Use other methods |
Such as a comparison of results with those of an alternative method validated using metrological traceable calibration, as specified in ISO 17511 |
| 328 |
7.3.7.2 c 3 |
Use other methods |
Like a re-examination of stored patient samples |
| 329 |
7.3.7.2 d |
Perform IQC at a defined frequency |
Regarding the stability and robustness of the examination method and the risk of harm to the patient in the event of an erroneous result |
| 330 |
7.3.7.2 e |
Record resulting data |
In order to detect trends and shifts, cf. § 8.4 |
| 331 |
7.3.7.2 e |
Apply statistical techniques, where applicable |
In order to review the results |
| 332 |
7.3.7.2 f |
Review CQI data against defined acceptance criteria at regular intervals |
Within a timeframe that allows for meaningful, real-time performance information |
| 333 |
7.3.7.2 g |
Prevent the reporting of patient results |
In the event that the CQI does not meet the defined acceptability criteria |
| 334 |
7.3.7.2 g 1 |
Reject results |
In the event that the defined acceptability criteria for IQC are not met (the results likely contain clinically significant errors) |
| 335 |
7.3.7.2 g 1 |
Re-examine patient samples |
After the error has been corrected, cf. § 7.5 |
| 336 |
7.3.7.2 g 2 |
Evaluate the results from patient samples |
Based on examinations since the last satisfactory IQC |
| |
7.3.7.3
|
External quality assessment (EQA)
|
|
| 337 |
7.3.7.3 a |
Monitoring performance regarding examination methods in relation to the results of other laboratories |
Such as participation in external quality assessment (EQA) programs and the interpretation of examination results, including POCT methods, cf. Annex A |
| 338 |
7.3.7.3 b |
Establish a procedure for registration, participation and performance of EQA |
For the examination methods used, where applicable (available programs), cf. § 8.3.1 |
| 339 |
7.3.7.3 c |
Process external quality assessment samples |
By the personnel performing pre-examination, examination, and post-examination procedures |
| 340 |
7.3.7.3 d 1 |
Enable verification of pre-examination, examination, and post-examination processes |
Regarding the selected EQA program(s), cf. §§ 7.2, 7.3 and 7.4 |
| 341 |
7.3.7.3 d 2 |
Provide samples that mimic patient samples in order to obtain clinically relevant challenges |
Regarding the selected EQA program(s) |
| 342 |
7.3.7.3 d 3 |
Fulfill ISO/IEC 17043 requirements |
Regarding EQA program(s) |
| 343 |
7.3.7.3 e |
Consider the type of target value offered |
Regarding selected EQA program(s) |
| 344 |
7.3.7.3 e 1 |
Ensure that target values are selected |
Independently, using a reference method. Consensus values can be used to determine whether shifts are attributable to the laboratory or the method |
| 345 |
7.3.7.3 e 2 |
Ensure that target values are selected |
By overall consensus data |
| 346 |
7.3.7.3 e 3 |
Ensure that target values are selected |
Based on consensus data defined for the peer group corresponding to the method used |
| 347 |
7.3.7.3 e 4 |
Ensure that target values are selected |
By a panel of experts. It may be useful to compare methods using switchable EQA materials |
| 348 |
7.3.7.3 f |
Use other methods to monitor the performance of the examination method
|
In cases where an EQA program is unavailable or unsuitable. Examples of acceptable alternative methods:
- participation in sample exchanges with other laboratories
- inter-laboratory comparison of results from analyzing the same IQC materials
- analysis using a different lot of the manufacturer's end-user calibrator
- blind analysis of microorganisms in the same sample:
- by two individuals
- on two analyzers
- using two methods
- analysis of reference materials considered commutable with patient samples
- analysis of patient samples from clinical correlation studies
- examination of cell and tissue bank materials
|
| 349 |
7.3.7.3 f |
Provide a justification for the choice of an alternative method |
And demonstrate the effectiveness of this examination method, cf. § 8.4 |
| 350 |
7.3.7.3 g |
Review EQA data at regular intervals against specified acceptance criteria and within a set time frame |
In order to obtain meaningful information on real-time performance |
| 351 |
7.3.7.3 h |
Implement appropriate action, including an assessment of the clinical impact of nonconformity related to patient samples |
In cases where EQA results do not meet specified acceptance criteria, cf. § 8.7 |
| 352 |
7.3.7.3 i |
Review the examination results of the patients concerned |
When the clinical impact is significant |
| 353 |
7.3.7.3 i |
Consider the need for an amendment |
And advise users, as appropriate |
| |
7.3.7.4
|
Comparability of examination results
|
|
| 354 |
7.3.7.4 a |
Specify a procedure to establish the comparability of patient sample results across appropriate clinical intervals |
Specifically in cases where different methods or equipment are used for the same examination, or where the examination is performed at different sites. Patient samples should be used to compare examination methods., cf. § 8.3.1 |
| 355 |
7.3.7.4 b |
Record comparability results and make them available |
Cf. § 8.4 |
| 356 |
7.3.7.4 c |
Review the comparability of results |
Regularly |
| 357 |
7.3.7.4 d |
Assess the impact of the identified differences |
On biological reference intervals and clinical decision limits |
| 358 |
7.3.7.4 d |
Take appropriate action |
When differences are identified |
| 359 |
7.3.7.4 e |
Inform users of any clinically significant difference |
Regarding the comparability of results |
| |
7.4
|
Post-examination processes
|
|
| |
7.4.1
|
Reporting of results
|
|
| |
7.4.1.1
|
General
|
|
| 360 |
7.4.1.1 a |
Report examination results accurately, clearly, and unambiguously |
And in accordance with the instructions of the examination procedure.cf. § 8.4 |
| 361 |
7.4.1.1 a |
Include all information necessary for the interpretation of results |
And for traceability between the examination request and the report |
| 362 |
7.4.1.1 b |
Establish a procedure to alert users in case of delays in communicating examination reports |
Based on the impact of the delay on patient care, cf. § 8.3.1 |
| 363 |
7.4.1.1 c |
Retain all information associated with reports |
In accordance with management system requirements, cf. § 8.4 |
| |
7.4.1.2
|
Result review and release
|
 |
| 364 |
7.4.1.2 |
Review and authorize results |
Prior to any release |
| 365 |
7.4.1.2 |
Ensure that authorized personnel review the examination results and evaluate them against IQC results |
Available clinical information, and previous examination results |
| 366 |
7.4.1.2 |
Specify the responsibilities and procedures regarding the arrangements for releasing examination results |
Specifically, by whom and to whom, cf. § 8.3.1 |
| |
7.4.1.3
|
Critical result reports
|
|
| 367 |
7.4.1.3 a |
Notify the user or any other person authorized to be informed as soon as appropriate, based on clinical information available |
When examination results fall within critical decision limits |
| 368 |
7.4.1.3 b |
Document the actions taken, the date, the time, the person responsible, the person notified, the results transmitted, the verification of the accuracy of the information communicated |
And any difficulties related to the notification |
| 369 |
7.4.1.3 c |
Have an appeals procedure in place for staff |
When the person in charge cannot be reached, cf. § 8.3.1 |
| |
7.4.1.4
|
Special considerations for results
|
|
| 370 |
7.4.1.4 a |
Make any information from the reports that was not transmitted to the user easily accessible |
Cf. §§ 7.4.1.6 and 7.4.1.7 |
| 371 |
7.4.1.4 b |
Provide systematically the final report to the user |
When results are transmitted as a preliminary (partial) report |
| 372 |
7.4.1.4 c |
Maintain records of all results communicated orally |
Including details of the verification of the accuracy of the information communicated, cf. § 8.4 |
| 373 |
7.4.1.4 c |
Ensure that these results are always included in a report |
Cf. § 8.4 |
| |
7.4.1.5
|
Automated selection, review, release and reporting of results
|
|
| 374 |
7.4.1.5 a |
Establish a procedure ensuring that the criteria for automatic selection, review, and release are specified, approved, accessible, and understandable to the personnel authorizing the release of results |
Applicable when the laboratory uses an automated system for the selection, review, release, and reporting of results, cf. § 8.3.1 |
| 375 |
7.4.1.5 b |
Establish a procedure ensuring that criteria are validated and approved prior to use, and reviewed and verified whenever the automated system is modified |
Applicable when the laboratory uses an automated system for the selection, review, release and reporting of results, cf. § 8.3.1 |
| 376 |
7.4.1.5 c |
Establish a procedure ensuring that results selected by the automated system for manual review are identifiable |
Applicable when the laboratory uses an automated system for the selection, review, release and reporting of results, cf § 8.3.1. If necessary, the date and time of selection and review, as well as the person who performed the review, are retrievable |
| 377 |
7.4.1.5 d |
Establish a procedure that includes the possibility that, if necessary, the automated selection, review, release and reporting of results can be quickly suspended |
When the laboratory uses an automated system for the selection, review, release and reporting results, cf. § 8.3.1 |
| |
7.4.1.6
|
Requirements for reports
|
|
| 378 |
7.4.1.6 a |
Include the following on every page of any report, unless valid reasons for omitting information are documented |
Patient identification, date of primary sample collection and report date |
| 379 |
7.4.1.6 b |
Include the following on every page of any report, unless valid reasons for omitting information are documented |
Identification of the laboratory issuing the report |
| 380 |
7.4.1.6 c |
Include the following on every page of any report, unless valid reasons for omitting information are documented |
Name or other unique identifier of the user |
| 381 |
7.4.1.6 d |
Include the following on every page of any report, unless valid reasons for omitting information are documented |
The type of primary sample and all sample-specific information (nature, macroscopic description) |
| 382 |
7.4.1.6 e |
Include the following on every page of any report, unless valid reasons for omitting information are documented |
Clear identification of the examinations performed |
| 383 |
7.4.1.6 f |
Include the following on every page of any report, unless valid reasons for omitting information are documented |
The examination methods used, and, where relevant, the harmonized identification of the measurand and the measurement principle |
| 384 |
7.4.1.6 g |
Include the following on every page of any report, unless valid reasons for omitting information are documented |
Examination results in SI units of measurement, where appropriate, or traceable to SI or other units |
| 385 |
7.4.1.6 h |
Include the following on every page of any report, unless valid reasons for omitting information are documented |
Biological reference intervals, clinical decision limits, likelihood ratios, and diagrams with defined clinical decision limits |
| 386 |
7.4.1.6 i |
Include the following on every page of any report, unless valid reasons for omitting information are documented |
Identification of examinations performed as part of a research or development program, without information on measurement performance |
| 387 |
7.4.1.6 j |
Include the following on every page of any report, unless valid reasons for omitting information are documented |
The person who reviewed the results and authorized the release of the report (if this information is missing, it is easily accessible) |
| 388 |
7.4.1.6 k |
Include the following on every page of any report, unless valid reasons for omitting information are documented |
Identification of all results considered as preliminary |
| 389 |
7.4.1.6 l |
Include the following on every page of any report, unless valid reasons for omitting information are documented |
Indication of any critical results |
| 390 |
7.4.1.6 m |
Include the following on every page of any report, unless valid reasons for omitting information are documented |
Unique identification of a complete report, clear indication of the end (page number to total number of pages) |
| |
7.4.1.7
|
Additional information for reports
|
|
| 391 |
7.4.1.7 a |
Include the time of primary sample collection |
If necessary for patient care |
| 392 |
7.4.1.7 b |
Keep the date of release of the minutes available for consultation |
If this date does not appear in the report |
| 393 |
7.4.1.7 c |
Keep available the identification of examinations performed by the subcontracting laboratory |
Including unmodified consultant information and the laboratory performing the tests |
| 394 |
7.4.1.7 d 1 |
Include in the report, where relevant, an interpretation of the results and comments |
Regarding the quality and nature of the sample that could potentially lead to a misinterpretation of the examination results |
| 395 |
7.4.1.7 d 2 |
Retain all information associated with the reports |
Regarding differences between results (examinations performed using other methods or at other sites), cf. § 8.4 |
| 396 |
7.4.1.7 d 3 |
Retain all information associated with the reports |
Regarding the risk of misinterpretation caused by the use of multiple units of measurement, cf. § 8.4 |
| 397 |
7.4.1.7 d 4 |
Retain all information associated with the reports |
Regarding the trend in results or significant changes over a given period, cf. § 8.4 |
| |
7.4.1.8
|
Amendments to reported results
|
|
| 398 |
7.4.1.8 a |
Ensure that procedures for releasing revised or modified results include recording the reason for the modification |
And including it in the revised report, cf. § 8.3.1 |
| 399 |
7.4.1.8 b |
Ensure that procedures for releasing revised or modified results include providing the revised results as a supplementary document or an additional data transfer |
And that they are clearly identified as revised. Also included are the date and patient identity from the original report, cf. § 8.4 |
| 400 |
7.4.1.8 c |
Ensure that procedures for releasing revised or modified results include information about the revision |
To the user, cf. § 8.3.1 |
| 401 |
7.4.1.8 d |
Ensure that procedures for releasing revised or modified results include, for the issuance of a new complete report |
A unique identifier and a reference to the initial report being replaced, cf. § 8.3.1 |
| 402 |
7.4.1.8 e |
Ensure that procedures for releasing revised or modified results include a retained record of these revisions |
When the reporting system cannot capture revisions |
| |
7.4.2
|
Post-examination handling of samples
|
|
| 403 |
7.4.2 |
Specify the duration and conditions for sample storage |
After examination, cf. § 8.4 |
| 404 |
7.4.2 a |
Ensure that after the examination |
The patient identity and source of the sample are preserved., § 8.4 |
| 405 |
7.4.2 b |
Ensure that after the examination |
The possibility of subjecting the sample to additional examinations is known |
| 406 |
7.4.2 c |
Ensure that after the examination |
The sample is stored in such a way that additional examinations can be performed |
| 407 |
7.4.2 d |
Ensure that after the examination |
The sample can be located and retreived |
| 408 |
7.4.2 e |
Ensure that after the examination |
The sample is discarded appropriately |
| |
7.5
|
Nonconforming work
|
|
| 409 |
7.5 |
Have a process in place for cases where an aspect of laboratory activities or examination results does not conform |
To its own procedures, quality specifications, or user requirements, cf. § 8.2.4 |
| 410 |
7.5 a |
Ensure that the process includes |
The responsibilities and authorities for the management of nonconforming work, cf. § 8.2.4 |
| 411 |
7.5 b |
Ensure that the process includes |
Immediate and long-term actions based upon the risk analysis process, cf. §§ 8.2.4, 8.5 and 8.7 |
| 412 |
7.5 c |
Ensure that the process includes |
When there is a risk of harm to patients, examinations are halted and reports are not released, cf. § 8.2.4 |
| 413 |
7.5 d |
Ensure that the process includes |
An evaluation of the significance of the nonconforming work is carried out, including an analysis of the impact of examination results released prior to the identification of the nonconformity., cf. § 8.2.4 |
| 414 |
7.5 e |
Ensure that the process includes |
The decision on the acceptability of the nonconforming work, cf. § 8.2.4 |
| 415 |
7.5 f |
Ensure that the process includes |
The review of examination results, when necessary, notification to the user, cf. § 8.2.4 |
| 416 |
7.5 g |
Ensure that the process includes |
The responsibility for authorizing the resumption of work, cf. § 8.2.4 |
| 417 |
7.5 |
Implement corrective action |
Commensurate with the risk of recurrence of the nonconforming work, cf. § 8.7 |
| 418 |
7.5 |
Retain records of nonconforming work and actions implemented |
Cf. §§ 8.4 and 8.7 |
| |
7.6
|
Control of data and information management
|
|
| |
7.6.1
|
General
|
|
| 419 |
7.6.1 |
Have access to the necessary data and information is essential for carrying out laboratory activities |
ISO 22367 provides details on the risks associated with IT systems for medical biology laboratories. Annex A of ISO 27001 provides details on referencing information security measures. Documentation is also presented in the § 8.2.4 |
| |
7.6.2
|
Authorities and responsibilities for information management
|
|
| 420 |
7.6.2 |
Ensure that authorities and responsibilities for information system management are specified |
Including the maintenance and modification of information systems that could affect patient care. Ultimate responsibility for laboratory information systems rests with top management. cf. §§ 4.2.1 and 5.2.2 |
| |
7.6.3
|
Information systems management
|
|
| 421 |
7.6.3 a |
Validate the information system with the supplier and verify it in the laboratory prior to commissioning, including its compatibility with other laboratory systems |
The information system regarding examination data and information includes:
- collection
- processing
- recording
- reporting
- storage
- retrieval
|
| 422 |
7.6.3 a |
Authorize, document, and validate any system change prior implementation |
Including changes regarding software configuration or off-the-shelf commercial software
|
| 423 |
7.6.3 b |
Document the information system |
And keep it readily available to authorized users, including for day-to-day operations
|
| 424 |
7.6.3 c |
Implement the information system |
Including consideration of cybersecurity to protect the system against unauthorized access, tampering, or data loss |
| 425 |
7.6.3 d |
Use the information system in an environment that complies with the supplier's specifications |
Or, in the case of a non-computerized system, maintain the accuracy of manual records and their transcription |
| 426 |
7.6.3 e |
Maintain the information system to ensure the integrity of data and information |
And include recording system failures and corrective actions implemented, cf. § 8.7 |
| 427 |
7.6.3 |
Check calculations and data transfers |
In an appropriate and systematic manner
|
| |
7.6.4
|
Downtime plans
|
|
| 428 |
7.6.4 |
Have planned processes in place to maintain operations in the event of an information system failure |
That could affect laboratory activities, including the selection and generation of automated results reports. The business continuity plan and emergency procedures are also outlined in the § 7.8 |
| |
7.6.5
|
Off site management
|
|
| 429 |
7.6.5 |
Ensure that the external provider meets the applicable requirements of ISO 15189 (2022 version) |
When the laboratory information system is managed and maintained off-site |
| |
7.7
|
Complaints
|
|
| |
7.7.1
|
Process
|
|
430
|
7.7.1 |
Have a process "Manage complaints" |
Cf. §§ 8.2.4 and 8.6.2 |
| 431 |
7.7.1 a |
Include in process "Manage complaints" |
A description of the activities of receipt, substantiate and investigating the complaint (actions to be taken and opportunities to be seized), cf. §§ 8.7.1 and 8.6 |
| 432 |
7.7.1 b |
Include in process "Manage complaints" |
Tracking and recording of the complaint and the actions taken, cf. §§ 8.4 and 8.7.1 |
| 433 |
7.7.1 c |
Include in process "Manage complaints" |
Ensuring appropriate action is taken, cf. § 8.7.1 |
| 434 |
7.7.1 |
Keep the complaint handling process description |
Available to users, cf. § 8.2.4 |
| |
7.7.2
|
Receipt of complaint
|
|
| 435 |
7.7.2 a |
Confirm that the complaint is related to laboratory activities |
Upon receipt of the complaint |
| 436 |
7.7.2 a |
Treat the complaint |
In order to resolve the complaint, cf. § 8.7.1 |
| 437 |
7.7.2 b |
Taking responsibility |
Regarding the collection of information to determine whether the complaint is substantiated |
| 438 |
7.7.2 c |
Acknowledge receipt of the complaint |
And provide the complainant with the findings and, where relevant, a progress report, cf. § 8.4 |
| |
7.7.3
|
Resolution of complaint
|
|
| 439 |
7.7.3 |
Do not give rise to discriminatory actions |
Regarding the review and handling of complaints |
| 440 |
7.7.3 |
Conduct, review, and approve the handling of complaints |
By persons not involved in the subject matter of the complaint |
| 441 |
7.7.3 |
Do not compromise impartiality for the sake of an alternative approach |
When resources are insufficient, cf § 4.1 |
| |
7.8
|
Continuity and emergency preparedness planning
|
|
| 442 |
7.8 |
Ensure that risks related to emergency situations are identified |
And that a business continuity plan (BCP) is established to allow operations to continue after an interruption (see § 8.4.1). Plans in case of failure are also presented in the § 7.6.4 |
| 443 |
7.8 |
Test regularly business continuity plans |
And the planned response capability, where possible |
| 444 |
7.8 a |
Implement measures to respond to emergency situations |
Taking into account the needs and available capabilities of the staff |
| 445 |
7.8 b |
Provide information and training |
To relevant personnel, cf. § 6.2.4 |
| 446 |
7.8 c |
Respond to actual emergency situations |
Cf. § 7.6.4 |
| 447 |
7.8 d |
Take action to prevent or mitigate the consequences of emergency situations |
Taking into account the scale of the emergency and the potential impact. Further details are available in CLSI GP36-A |
| |
8
|
Management system requirements
|
|
| |
8.1
|
General requirements
|
|
| |
8.1.1
|
General
|
|
| 448 |
8.1.1 |
Establish, document, implement, and maintain a management system |
In order to ensure and demonstrate compliance with the requirements of ISO 15189:2022 (when the laboratory performs POCTs, include them), cf. Annex A) |
| 449 |
8.1.1 |
Include in the management system, as a minimum |
The following points:
- responsibilities (§ 8.1)
- objectives and policies (§ 8.2)
- documentation (§§ 8.2, 8.3 and 8.4)
- actions to address risks (§ 8.5)
- continual improvement (§ 8.6)
- corrective actions (§ 8.7)
- evaluations and internal audits (§ 8.8)
- management review (§ 8.9)
|
| |
8.1.2
|
Fulfillment of management system requirements
|
|
| 450 |
8.1.2 |
Ensure and demonstrate that the quality management system complies with the requirements of ISO 15189 (2022 version) |
Included in clauses 4 to 7 and the sub-clauses.8.2 to 8.9 |
|
|
8.1.3
|
Management system awareness
|
|
| 451 |
8.1.3 a |
Ensure that personnel performing work under the laboratory's control are made aware of |
The laboratory's policies and objectives, cf. § 5.5 |
| 452 |
8.1.3 b |
Ensure that personnel performing work under the laboratory's control are made aware of |
Their contribution to the effectiveness of the management system and to the benefits of performance improvement |
| 453 |
8.1.3 c |
Ensure that personnel performing work under the laboratory's control are made aware of |
The consequences of not conforming with the management system requirements |
| |
8.2
|
Management system documentation
|
|
| |
8.2.1
|
General
|
|
| 454 |
8.2.1 |
Establish, document, and maintain policies and objectives |
In order to meet the requirements of ISO 15189 (2022 version). Top management responsibility. A quality manual is not mandatory and may be replaced by a commercial brochure, cf. § 8.2.3. The objectives and policies are also presented in § 5.5 |
| 455 |
8.2.1 |
Ensure that policies and objectives are known and applied |
At all levels of the laboratory organization, cf. § 5.5 |
| |
8.2.2
|
Competence and quality
|
|
| 456 |
8.2.2 |
Include in objectives and policies competence, quality |
And consistent operation of the laboratory, cf. § 8.2.3 |
| |
8.2.3
|
Evidence of commitment
|
|
| 457 |
8.2.3 |
Provide evidence that top management is committed to the development and implementation of the management system |
And improvement of its effectiveness, cf. § 8.6.1. Examples of policies (good practices) : 
- quality policy (§ 5.2.2)
- personnel management (§ 6.2)
- continuing education (§ 6.2.4)
- safety and environmental conditions (§ 6.3)
- equipment management (§ 6.4)
- management of reagents and consumables (§ 6.6)
- supplier management (§§ 6.7 and 6.8)
- sample collection (§ 7.2.4)
- sample transport (§ 7.2.5)
- result validation (§ 7.3.7)
- communication (§ 7.4)
- reporting of results (§ 7.4.1)
- archiving of sample results (§ 7.4.2)
- risk management (§ 8.5)
- continual improvement (§ 8.6.1)
- management of nonconformities (§ 8.7.1)
- management review (§ 8.9)
|
| |
8.2.4
|
Documentation
|
|
| 458 |
8.2.4 |
Include in the management system all documents, processes, systems, and records relating to the fulfillment of the requirements of ISO 15189 (2022 version) |
Being referenced or having a link to the management system, cf. §§ 8.3 and 8.4. Data control and information management are also presented in § 7.6. Often used processes : 
- manage patient rights (§ 4.3)
- manage personnel (§ 6.2)
- manage facilities (§ 6.3)
- manage equipment (§ 6.4)
- manage reagents and consumables (§ 6.6)
- manage suppliers (§§ 6.7 and 6.8)
- collect samples (§ 7.2.4)
- transport samples (§ 7.2.5)
- receive samples (§ 7.2.6)
- secure samples (§ 7.2.7)
- validate examination methods (§ 7.3.3)
- perform internal quality control (§ 7.3.7.2)
- compare performance (§ 7.3.7.3)
- validate result reports (§ 7.4.1)
- retain samples (§ 7.4.2)
- control data (§ 7.6)
- manage business continuity (§§ 7.6.4; 7.8)
- manage complaints (§ 7.7)
- manage documentation (§§ 8.2, 8.3 and 8.4)
- address risks (§§ 5.6; 8.5)
- improve (§ 8.6.1)
- control nonconformities (§ 8.7.1)
- implement corrective actions (§ 8.7.2)
- conduct audits (§ 8.8.3)
- conduct management review (§ 8.9)
- govern POCTs (Annex A.2)
|
| |
8.2.5
|
Personnel access
|
|
| 459 |
8.2.5 |
Make the applicable management system documents available to laboratory personnel |
And also related information |
| |
8.3
|
Control of management system documents
|
|
| |
8.3.1
|
General
|
|
| 460 |
8.3.1 |
Control the internal and external documents |
Related to compliance with the requirements of ISO 15189 (2022 version). Interpret the term "document" in a broad sense. Recommended procedures: 
- Personnel management (§ 6.2)
- Facility management (§ 6.3)
- Equipment management (§ 6.4)
- Calibration and metrological traceability (§ 6.5)
- Reagent and consumable management (§ 6.6)
- Contract management (§ 6.7)
- External providers (§ 6.8)
- Patient and user information management (§ 7.2.2)
- Examination request management (§ 7.2.3)
- Sample collection (§ 7.2.4.1)
- Sample identification and labeling (§ 7.2.4.2)
- Sample transport (§ 7.2.5)
- Sample receipt (§ 7.2.6.1)
- Pre-examination handling (§ 7.2.7)
- Verification of examination methods (§ 7.3.2)
- Validation of examination methods (§ 7.3.3)
- Biological reference intervals (§ 7.3.5)
- Examination procedures (§ 7.3.6)
- Validity of examination results (§ 7.3.7.1)
- Internal quality control (§ 7.3.7.2)
- External quality assessment (§ 7.3.7.3)
- Internal and external communication (§ 7.4)
- Nonconforming work (§ 7.5)
- Data control (§ 7.6)
- Complaint management (§ 7.7)
- Document control (§§ 8.2; 8.3)
- Record control (§ 8.4)
- Risk and opportunity management (§ 8.5)
- Continual improvement (§ 8.6.1)
- Nonconformity management (§ 8.7.1)
- Corrective actions (§ 8.7.2)
- Internal audits (§ 8.8.3)
- Management review (§ 8.9.1)
- Point-of-care medical biology testing (Annex A)
|
| |
8.3.2
|
Control of documents
|
|
| 461 |
8.3.2 a |
Ensure that documents are identified |
In an unique manner (codification) |
| 462 |
8.3.2 b |
Ensure the suitability of the documents has been approved prior to their release |
By authorized personnel (possessing the necessary expertise and skills) |
| 463 |
8.3.2 c |
Ensure that documents are periodically reviewed |
And updated, if necessary |
| 464 |
8.3.2 d |
Ensure that the relevant versions of documents are available where they are used |
And that their distribution is controlled, if necessary |
| 465 |
8.3.2 e |
Ensure that document changes are identified |
Including the current revision status |
| 466 |
8.3.2 f |
Ensure that documents are protected against unauthorized modifications |
Including any erasure or deletion |
| 467 |
8.3.2 g |
Ensure documents are protected |
Against unauthorized access |
| 468 |
8.3.2 h |
Ensure that the use of obsolete documents is prevented |
Including ensuring that such documents are correctly identified |
| 469 |
8.3.2 i |
Ensure that a paper or electronic version of the obsolete document is retained for a defined period |
Or in accordance with regulatory requirements |
| |
8.4 |
Control of records |
|
| |
8.4.1 |
Creation of records
|
|
| 470 |
8.4.1 |
Establish and maintain legible records |
In order to demonstrate compliance with the requirements of ISO 15189 (2022 version). Implicit and explicit records: 
- declaration of no conflict of interest (§ 4.1)
- confidentiality agreement (§ 4.2.3)
- patient needs and expectations (§§ 4.3; 8.6.2)
- legal status (§ 5.1)
- laboratory director role (§§ 5.2.2; 8.2.3)
- scope (§ 5.3.1)
- compliance register (§ 5.3.2)
- advisory services (§ 5.3.3)
- organizational chart (§ 5.4.1)
- duty schedule (§ 5.4.1)
- quality policy (§ 5.5)
- welcome handbook (§ 6.2.1)
- job description (§ 6.2.1)
- competency matrix (§ 6.2.2)
- personnel authorization register (§ 6.2.3)
- training register (§ 6.2.4)
- personnel file (§ 6.2.5)
- authorization record (§ 6.2.5)
- facilities register (§ 6.3.2)
- cleaning and disinfection (§ 6.3.3)
- waste register (§ 6.3.3)
- pest prevention and control (§ 6.3.3)
- temperature log (§ 6.3.5; 6.6.4)
- equipment register (§ 6.4.1)
- equipment maintenance program (§ 6.4.5)
- calibration certificate register (§ 6.5.2)
- reagents and consumables register (§ 6.6.7)
- supplier contracts (§§ 6.7.1; 6.8.1)
- supplier evaluations (§ 6.8.2)
- register of supplied products and services by external providers (§ 6.8.3)
- communication to patients (§ 7.2.2)
- log of examination requests (§ 7.2.3)
- log of sample collections (§ 7.2.4)
- sample labeling records (§ 7.2.4.2)
- log of sample transport (§ 7.2.5)
- log of sample receipt (§ 7.2.6)
- log of pre-examination handling (§ 7.2.7)
- method verification reports (§ 7.3.2)
- method validation reports (§ 7.3.3)
- measurement uncertainty evaluations (§ 7.3.4)
- record of reference intervals (§ 7.3.5)
- list of examination procedures (§ 7.3.6)
- record of examination result validity (§ 7.3.7)
- record of internal quality controls (§ 7.3.7.2)
- record of external quality assessments (7.3.7.3)
- comparability results (§ 7.3.7.4)
- result reports (§ 7.4.1)
- orally communicated results (§ 7.4.1.4)
- sample results archive register (§ 7.4.2)
- nonconforming results (§ 7.5)
- root causes of nonconformities (§ 7.5)
- data access log (§ 7.6.2)
- data backup log (§ 7.6.3)
- business continuity plan (§ 7.6.4; 7.8)
- record of BCP tests (§ 7.6.4; 7.8)
- complaints log (§ 7.7.2)
- list of documents (§§ 8.2; 8.3; 8.4)
- risk register (§ 8.5)
- opportunities for improvement (§ 8.6.1)
- nonconformities and corrective actions (§ 8.7.3)
- quality meeting minutes (§ 8.8.1)
- quality indicators (§ 8.8.2)
- audit program and reports (§ 8.8.3)
- list of auditors (§ 8.8.3)
- management review minutes (§ 8.9.3)
- contracts with POCT sites (Annex A.2)
- POCT site register (Annex A.2)
- POCT equipment register (Annex A.2)
- POCT sample register (Annex A.2)
- POCT site audit report (Annex A.3)
- POCT training register (Annex A.4)
|
| 471 |
8.4.1 |
Create records for each activity that could affect the quality of an examination |
At the time the activity is performed. A record may take any form or type |
| |
8.4.2 |
Amendment of records
|
|
| 472 |
8.4.2 |
Ensure that record modifications can be traced back to previous versions |
or to the original observations |
| 473 |
8.4.2 |
Retain original and modified data and files |
Including the date and time of the modification, the aspects modified, and the person who made the modification, where relevant. The retention period must comply with applicable regulations and cannot be less than two years |
|
|
8.4.3 |
Retention of records
|
|
| 474 |
8.4.3 a |
Implement the procedures needed for record control |
Record control includes, cf. § 8.3.1
- identification
- storage
- protection (unauthorized access or modification)
- backup
- archive
- retrieval
- retention period
- disposal of
|
| 475 |
8.4.3 b |
Specify the record retention period |
The retention period may depend on identified risks or legal liability |
| 476 |
8.4.3 c |
Keep result reports available for consultation |
For as long as necessary (or required) |
| 477 |
8.4.3 d |
Keep all records accessible throughout the retention period |
Ensure they are readable regardless of the medium and available for management review, cf. § 8.9 |
| |
8.5 |
Actions to address risks and opportunities for improvement
|
|
| |
8.5.1 |
Identification of risks and opportunities for improvement
|
|
| 478 |
8.5.1 a |
Identify risks and opportunities for improving laboratory activities |
In order to prevent or reduce adverse effects and potential failures. Risk management is also presented in § 5.6 |
| 479 |
8.5.1 b |
Identify risks and opportunities for improving laboratory activities |
In order to drive improvement by seizing opportunities for enhancement |
| 480 |
8.5.1 c |
Identify risks and opportunities for improving laboratory activities
|
In order to ensure that the management system has achieved the intended resultsCf. § 5.5 |
| 481 |
8.5.1 d |
Identify risks and opportunities for improving laboratory activities |
In order to reduce risks related to patient care, cf. § 5.6 |
| 482 |
8.5.1 e |
Identify risks and opportunities for improving laboratory activities |
In order to achieve the laboratory's objectives, cf. § 5.5 |
| |
8.5.2 |
Acting on risks and opportunities for improvement
|
|
| 483 |
8.5.2 |
Prioritize identified risks |
And control them, cf. § 5.5 |
| 484 |
8.5.2 |
Ensure that actions taken to address risks are proportionate to the impact on examination results |
And the safety of patients and staff |
| 485 |
8.5.2 |
Record decisions made and actions implemented |
In response to risks and opportunities for improvement |
| 486 |
8.5.2 |
Integrate and implement actions within the management system to address identified risks and opportunities |
And evaluate their effectiveness. Further details regarding risks can be found in ISO 22367 and ISO 35001 |
| |
8.6 |
Improvement
|
|
| |
8.6.1 |
Continual improvement |
|
| 487 |
8.6.1 a |
Improve continually the effectiveness of the management system in accordance with objectives and policies |
Including pre-examination, examination, and post-examination processes, cf. § 5.5 |
| 488 |
8.6.1 b |
Identify and select improvement opportunities |
And develop, document and implement necessary actions |
| 489 |
8.6.1 b |
Focus improvement activities on priority areas following the risk assessment |
Cf. § 8.5 |
| 490 |
8.6.1 c |
Evaluate the effectiveness of actions implemented |
Cf. § 8.5.2 |
| 491 |
8.6.1 d |
Ensure the laboratory participates in continual improvement activities |
This is a top management responsibility and covers relevant areas and patient care outcomes |
| 492 |
8.6.1 e |
Communicate top management's improvement plans |
And associated objectives to the staff |
| |
8.6.2 |
Laboratory patients, user, and personnel feedback
|
|
| 493 |
8.6.2 |
Seek feedback |
From patients, users and personnel |
| 494 |
8.6.2 |
Analyze and utilize feedback |
In ordre to improve the management system, laboratory activities, and services for users |
| 495 |
8.6.2 |
Retain records of feedback |
And implemented actions |
| 496 |
8.6.2 |
Communicate to personnel on actions taken |
Following feedback from personnel |
| |
8.7 |
Nonconformities and corrective actions
|
|
| |
8.7.1 |
Actions when nonconformity occurs
|
|
| 497 |
8.7.1 a 1 |
Respond to the nonconformity |
And react to control it. Nonconformities related to the execution of laboratory activities (pre-examination, examination and post-examination processes and associated resources) are also presented in the § 7.5 |
| 498 |
8.7.1 a 2 |
Respond to the nonconformity |
And addressing the consequences, including managing patient safety and informing the person concerned |
| 499 |
8.7.1 b |
Determine the causes of nonconformity |
Finding the root cause is not always straightforward |
| 500 |
8.7.1 c 1 |
Evaluate the need to implement corrective action by examining and analyzing the nonconformity |
In order to eliminate the root cause and significantly reduce the likelihood of recurrence |
| 501 |
8.7.1 c 2 |
Evaluate the need to implement corrective action by looking for similar nonconformities |
In order to eliminate the root cause and significantly reduce the likelihood of recurrence |
| 502 |
8.7.1 c 3 |
Evaluate the need for corrective action by evaluating the potential risks of the nonconformity |
In order to eliminate the root cause and significantly reduce the likelihood of recurrence |
| 503 |
8.7.1 d |
Implement all actions needed |
When nonconformity occurs |
| 504 |
8.7.1 e |
Review any corrective action taken |
And evaluate its effectiveness, cf. § 8.7.2 |
| 505 |
8.7.1 f |
Update risks and opportunities, as needed |
Cf. § 5.6 |
| 506 |
8.7.1 g |
Make changes to the management system |
If it is necessary |
| |
8.7.2 |
Corrective action effectiveness
|
|
| 507 |
8.7.2 |
Ensure that corrective actions are proportionate to the consequences of the nonconformities |
Cf. § 8.7.1 a 2. A cause that cannot be eliminated will be mitigated |
| 508 |
8.7.2 |
Ensure that corrective actions mitigate the identified causes |
Cf. § 8.7.1 b |
| |
8.7.3 |
Records of nonconformities and corrective actions
|
|
| 509 |
8.7.3 a |
Retain records of nonconformities as evidence |
Of the nature of the nonconformities, the causes and the actions implemented, cf. § 8.4 |
| 510 |
8.7.3 b |
Retain records of nonconformities as evidence |
Of the effectiveness of actions taken |
| |
8.8 |
Evaluations
|
|
| |
8.8.1 |
General
|
|
| 511 |
8.8.1 |
Conduct evaluations at scheduled intervals |
In order to demonstrate that all laboratory activity processes meet the requirements of patients, users and ISO 15189 (2022 version) |
| |
8.8.2 |
Quality indicators
|
|
| 512 |
8.8.2 |
Plan the process "Monitor quality indicators" |
Including the facility, see 8.2.4:
- objectives
- methodology
- interpretation
- limitations
- action plan
- duration of monitoring
|
| 513 |
8.8.2 |
Review periodically the indicators |
In order to ensure continued appropriateness |
| |
8.8.3 |
Internal audits
|
|
| 514 |
8.8.3.1 a |
Conduct internal audits at planned intervals |
In order to determine whether the management system conforms to the laboratory's requirements (its management system and its activities). The audits cover all laboratory activities, including POCT |
| 515 |
8.8.3.1 b |
Conduct internal audits at planned intervals |
In order to determine whether the management system complies with the requirements of ISO 15189 (2022 version) |
| 516 |
8.8.3.1 c |
Conduct internal audits at planned intervals |
In order to determine whether the management system is effectively implemented and maintained |
| 517 |
8.8.3.2 a |
Plan, establish, implement and maintain an audit program that includes |
Priority given to risks to patients (from laboratory activities) |
| 518 |
8.8.3.2 b |
Plan, establish, implement and maintain an audit program that includes |
Consideration of:
- identified risks
- external evaluations
- previous internal audits
- occurred nonconformities
- incidents
- complaints
- changes to laboratory activities
|
| 519 |
8.8.3.2 c |
Plan, establish, implement and maintain an audit program that includes |
The objectives, criteria, and scope of each audit. External auditors may participate in the audits, cf. §§ 4.2.3 and 6.8 |
| 520 |
8.8.3.2 d |
Plan, establish, implement and maintain an audit program that includes |
The selection of auditors (trained and qualified) who are independent of the activity being audited |
| 521 |
8.8.3.2 e |
Plan, establish, implement and maintain an audit program that includes |
The guarantee of objectivity and impartiality in audit activities |
| 522 |
8.8.3.2 f |
Plan, establish, implement and maintain an audit program that includes |
Communicating the results to the individuals concerned |
| 523 |
8.8.3.2 g |
Plan, establish, implement and maintain an audit program that includes |
Implementation of corrective actions (person responsible, timeframe) |
| 524 |
8.8.3.2 h |
Plan, establish, implement and maintain an audit program that includes |
Retention of records (adherence to the audit program, audit report), cf. § 8.4 |
| |
8.9 |
Management review
|
|
| |
8.9.1 |
General
|
|
| 525 |
8.9.1 |
Review the management system at planned intervals |
In order to ensure it remains suitable, adequate, and effective, and complies with the requirements of ISO 15189 (2022 version). The maximum interval is two years, though it is typically one year |
| |
8.9.2 |
Review input
|
|
| 526 |
8.9.2 a |
Record management review inputs and include |
The status of actions from the previous management review, changes to the management system, changes in activities and the adequacy of resources, cf. § 8.4 |
| 527 |
8.9.2 b |
Record management review inputs and include |
Fulfilment of objectives, policies and procedures, cf. § 8.3.1 |
| 528 |
8.9.2 c |
Record management review inputs and include |
Results of process indicators, internal audits, nonconformity analysis, corrective actions and external audits. |
| 529 |
8.9.2 d |
Record management review inputs and include |
Feedback (patients, users, personnel) |
| 530 |
8.9.2 e |
Record management review inputs and include |
Quality assurance of the validity of results (evaluation of the monitoring of the validity of results) |
| 531 |
8.9.2 f |
Record management review inputs and include |
Effectiveness of actions to address risks |
| 532 |
8.9.2 g |
Record management review inputs and include |
Performance of external providers, cf. § 6.8 |
| 533 |
8.9.2 h |
Record management review inputs and include |
Results of interlaboratory comparison |
| 534 |
8.9.2 i |
Record management review inputs and include |
Evaluation of POCT activities, cf. Annex A |
| 535 |
8.9.2 j |
Record management review inputs and include |
Training and monitoring activities, cf. § 6.2.4 |
| |
8.9.3 |
Review output
|
|
| 536 |
8.9.3 a |
Record the outputs of the management review and include decisions and actions |
Regarding the effectiveness of the management system and processes |
| 537 |
8.9.3 b |
Record the outputs of the management review and include decisions and actions |
Regarding the improvement of laboratory activities in accordance with the requirements of ISO 15189 (2022 version) |
| 538 |
8.9.3 c |
Record the outputs of the management review and include decisions and actions |
Regarding provision of needed resources |
| 539 |
8.9.3 d |
Record the outputs of the management review and include decisions and actions |
Regarding improvement of services to patients and users |
| 540 |
8.9.3 e |
Record the outputs of the management review and include decisions and actions |
Regarding any new change |
| 541 |
8.9.3 |
Ensure that actions decided during the management review are carried out |
Within the planned timeframe |
| 542 |
8.9.3 |
Communicate decisions from management review to personnel |
Cf. § 8.4 |
| |
Annex A |
Additional requirements for Point-of-Care Testing (POCT)
|
|
| |
A.2 |
Governance
|
|
| 543 |
A.2 |
Assume responsibility for establishing processes to monitor the accuracy and quality of POCTs performed in-house |
On behalf of the organization's governing body (agreement between the laboratory and the healthcare professional) |
| 544 |
A.2 |
Specify and communicate internal responsibilities and authorities |
Regarding contracts with sites performing POCTs |
| 545 |
A.2 |
Approve POCT contracts from a financial perspective |
And, where relevant, the financial plan |
| 546 |
A.2 |
Ensure that POCT contracts cover the location where the POCT services are performed |
And can be managed, for example, by a medical advisory committee |
| |
A.3 |
Quality assurance program
|
|
| 547 |
A.3 |
Appoint a person with the appropriate training and experience as the Quality Manager for POCT |
In order to review and comply with the requirements of ISO 15189 (2022 version) regarding POCT |
| |
A.4 |
Training program
|
|
| 548 |
A.4 |
Appoint a person with the appropriate training and experience to manage the training and competency assessment |
Of personnel performing POCT procedures. Laboratory responsibility |
| 549 |
A.4 |
Establish, implement, and maintain a theoretical and practical program |
For personnel performing POCT tasks |
|
|
|
|
|